By Miranda Niemas, Nursing Student (BSN candidate)
Clinically reviewed by Amy Niemas, RN-BC, BSN, MSW
Last updated: October 13, 2026
How to Score and Document a PHQ-9 (Nursing Guide)
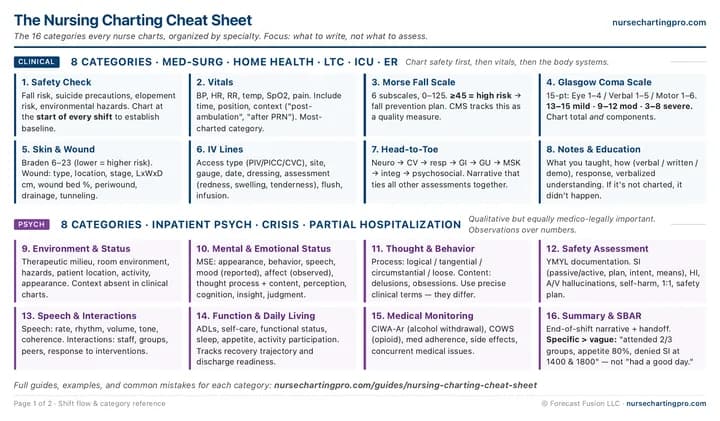
Get the free Nursing Charting Cheat Sheet
- All 16 charting categories, clinical and psych, with what to write for each
- Morse, Braden, Glasgow Coma Scale and SBAR at a glance
- The charting mistakes that cost nurses their licenses
Your med-surg admission involves a 38 year old woman recovering from a hysterectomy. The intake form is half-finished when the unit clerk hands you the PHQ-9 to complete. She scores a 14, with item 9 marked "several days." You stare at the screen, wondering whether to flag the total, the item 9 response, or both. I faced this exact scenario during my last clinical rotation. The framework that finally made it clear is to address item 9 first, then the total, while always considering functional impairment.
Why This Matters
Regulatory bodies: U.S. Preventive Services Task Force (USPSTF), American Academy of Family Physicians (AAFP), American Psychiatric Association (APA), Joint Commission - National Patient Safety Goal 15.01.01 (Suicide Risk Reduction), 988 Suicide and Crisis Lifeline (federally designated)
- The PHQ-9: validity of a brief depression severity measure — Kroenke K, Spitzer RL, Williams JB. J Gen Intern Med. 2001;16(9):606-613 (2001)
- Screening for Depression and Suicide Risk in Adults: US Preventive Services Task Force Final Recommendation — U.S. Preventive Services Task Force, June 20, 2023 (Grade B for adult depression screening) (2023)
- Depression Screening: A Practical Strategy — Maurer DM, Raymond TJ, Davis BN. Am Fam Physician. 2018;98(8):508-515 (2018)
- 988 Suicide and Crisis Lifeline (federally designated) — SAMHSA / Vibrant Emotional Health, 988 Suicide and Crisis Lifeline (2024)
- Practice Guideline for the Treatment of Patients With Major Depressive Disorder, Third Edition — American Psychiatric Association, October 2010 (2010)
- R3 Report Issue 18: National Patient Safety Goal for Suicide Prevention (NPSG 15.01.01) — The Joint Commission, November 2018 (effective July 1, 2019) (2018)
What the PHQ-9 Measures and Where It Is Used
The 9 Items, Walked Top Down
The PHQ-9 covers the nine DSM-aligned domains of major depressive disorder. Each item receives a rating from 0 to 3 based on the past 2 weeks: 0 (not at all), 1 (several days), 2 (more than half the days), 3 (nearly every day).
Item 1 - Anhedonia
Item 2 - Depressed Mood
Item 3 - Sleep Disturbance
Item 4 - Fatigue
Item 5 - Appetite Disturbance
Item 6 - Worthlessness or Guilt
Item 7 - Concentration
Item 8 - Psychomotor Changes
Item 9 - Thoughts of Self-Harm
Functional Impairment Item (Sometimes Called Item 10)
Scoring, Severity Bands, and the Functional Impairment Item
Item 9: The Suicidality Flag and What It Triggers
PHQ-2, PHQ-9, GAD-7: How the Screens Layer in Primary Care
PHQ-9 Documentation in NurseChartingPro
Common Mistakes
Charting Only the Total Without Breaking Out Item 9
PHQ-9 without the 9 component scores hides the most clinically important data point: item 9. The next reader of the chart cannot tell whether the moderate-range total includes a positive suicidality response without the component breakdown. Always chart the components and call out item 9 separately.
Treating PHQ-9 as a Diagnosis
The PHQ-9 serves as a screening tool, not a diagnostic measure. A score in the moderately severe range suggests major depression but does not confirm the diagnosis without a clinical interview. Documenting "patient has major depression" based solely on a PHQ-9 score overreaches and may require the next provider to correct.
Missing the Functional Impairment Item
The functional impairment question is essential for documentation completeness, even though it does not contribute to the score. Two patients with the same total can experience very different functional impacts. The impairment response distinguishes these differences in the chart and informs the clinical interview.
Scoring a Partial PHQ-9
You cannot score the PHQ-9 if any item is skipped. Document a partial PHQ-9 as such, without summing and labeling it with a severity band. A declined item 9 is a significant safety signal and should be documented and followed up like a positive response according to most institutional policies.
Using the Adult PHQ-9 on an Adolescent
The PHQ-9 is validated for adults. For pediatric populations, use the PHQ-A, which adapts the language for adolescents and includes two additional items: irritability and suicidality phrasing. Administering the adult PHQ-9 to a minor may yield a score that does not align with the validated thresholds for that age group.
Case Example
Scenario
As the day shift med-surg nurse caring for Mrs. Chen, a fictional 38 year old admitted overnight after a laparoscopic hysterectomy, I follow the unit's admission protocol, which includes a PHQ-9 for every patient. The night shift started the intake form, but they left the PHQ-9 section blank. I complete it with the patient at 1000, and the score returns 14, with item 9 marked "several days." The patient is alert, oriented, hemodynamically stable, and denies pain above 3 out of 10. She has no documented psychiatric history. The on-call provider is in a procedure for the next hour.
Chart Entry
1000 PHQ-9 Screening:

PHQ-9 total: 14 (moderate severity band).

Component scores (each 0-3, recall 2 weeks):
- Item 1 (anhedonia): 2 (more than half the days)
- Item 2 (depressed mood): 2 (more than half the days)
- Item 3 (sleep): 2 (more than half the days)
- Item 4 (fatigue): 2 (more than half the days)
- Item 5 (appetite): 1 (several days)
- Item 6 (worthlessness/guilt): 2 (more than half the days)
- Item 7 (concentration): 1 (several days)
- Item 8 (psychomotor): 1 (several days)
- Item 9 (thoughts of self-harm): 1 (several days) - POSITIVE

Functional impairment: "Very difficult" to do work, take care of things at home, or get along with other people.

Item 9 follow-up:
Bedside open-ended question: "Tell me more about that." Patient stated, "Sometimes I think my family would be better off without me, especially since the diagnosis. I have not thought about how I would do it." Denies current plan, denies access to means at home (no firearms, medications stored in locked cabinet per spouse). Spouse aware of recent mood changes and named as designated support contact. Patient agreed to a safety plan: notify spouse or call 988 if thoughts intensify; spouse to remove any prescription opioid bottles when patient is discharged.

Action taken:
- Provider notified via secure message at 1015.
- Behavioral health consult ordered, expected within 24 hours.
- Sitter not indicated at this time; environmental precautions reviewed (sharps secured, medication double locked).
- Patient education at the bedside: reviewed coping skills and stress-relief techniques (paced breathing, grounding, brief activity scheduling) with patient and spouse; reinforced safety plan and reasons-for-living list patient identified (children, recovery from surgery).
- Discharge resources provided in writing: 988 Suicide and Crisis Lifeline (call or text 988, chat at 988lifeline.org), outpatient mental health follow-up, and primary-care follow-up.
- Reassess PHQ-9 component item 9 (for suicidality) at 1400 and at every shift handoff until consult complete.
Key points from above chart entry
- Total + 9 component scores broken out:
- The total alone hides which specific items are positive. Listing all 9 components makes item 9 immediately visible to the next reader and supports the audit trail.
- Item 9 flagged separately and followed up:
- The standalone item 9 entry, the bedside follow-up question, and the safety plan together satisfy National Patient Safety Goal 15.01.01 documentation expectations. A positive item 9 without a documented follow-up is the worst pattern an audit can find.
- Functional impairment captured:
- The functional impairment field is required even though it does not score. "Very difficult" alongside a total of 14 communicates more clinical impact than the total alone.
- 988 Lifeline included in plan:
- The federally designated crisis line appears in the documented plan because the patient will eventually be discharged. The 988 reference is not a substitute for the inpatient response (consult, sitter, environmental precautions) but it is a required handoff resource.
- Reassessment frequency specified:
- Reassessing item 9 every shift until the behavioral health consult is complete is what closes the documentation loop. Charting a positive item 9 once and then never reassessing is a common gap an audit will catch.
Pro Tips
- Read Each Item Verbatim: Read every PHQ-9 item exactly as it appears on the screen. Do not paraphrase, summarize, or soften the wording (especially on item 9). Reading items in your own words changes their meaning and breaks the validation. Verbatim reading is also what keeps scores comparable across providers, clinicians, and nurses on the same patient.
- Read Item 9 First, Then the Total: Most nurses read from top to bottom: total, severity, and item 9 last. Reverse this habit. Item 9 carries clinical weight independent of the total. Reading it first indicates whether the chart entry requires a safety paragraph before mapping the severity band. Use the total for trend analysis; rely on item 9 for the next 30 minutes.
- What Makes the Score Valid: the 2-Week Recall Window: Read the recall window out loud to the patient: "Over the past 2 weeks, how often have you been bothered by the following problems?" The 2-week window is what makes the score map to DSM major-depression criteria. Patients who answer for "today" or "the past few months" produce a score that does not match the validated thresholds, and the score has to be readministered with the correct recall instructions.
- A Declined Item Is Not a Zero: When a patient declines an item (especially item 9), do not score it as 0 to make the math work. A declined item renders the total uncalculable and should be documented as a partial PHQ-9. Specifically, a declined item 9 is a significant safety signal; document the decline, note the follow-up, and let institutional policy determine whether to treat it as positive (most do).
- Pair PHQ-9 With GAD-7 When Anxiety Is in the Picture: Depression and anxiety are highly comorbid, and PHQ-9 alone misses the anxiety dimension. If the patient endorses worry, irritability, or restlessness during the bedside follow-up, the next administration to add is the GAD-7. The Kroenke 2009 PHQ-4 (combining PHQ-2 and GAD-2) is the ultra-brief equivalent if your unit uses entry-level screens.
- Differentiate Score from Diagnosis in Every Chart Entry: Chart "PHQ-9 score 18, moderately severe band, score consistent with possible major depression, clinical interview pending." Do not chart "patient has major depression." The score does not establish the diagnosis. The clinical interview that follows (performed by a provider or clinician, not the nurse) does. Keeping that distinction in your chart entry protects the next provider from having to walk back an overreach.
Step by Step
- Frame the 2-week recall window: Read the recall instructions aloud: "Over the past 2 weeks, how often have you been bothered by the following problems?" The 2-week window is what makes the score map to validated thresholds. Patients answering for "today" or "this month" produce a score that does not match the published interpretation.
- Score each item 0 to 3: Walk through items 1 to 9 with the patient. Score each item as follows: 0 (not at all), 1 (several days), 2 (more than half the days), or 3 (nearly every day). Document the patient's response verbatim when uncertain. Let the score reflect the patient's words, not your interpretation.
- Sum the score and identify the severity band: Add the 9 item scores to get a total from 0 to 27. Map the total: 0-4 minimal, 5-9 mild, 10-14 moderate, 15-19 moderately severe, 20-27 severe. A score of 10 or higher is the most common screening trigger.
- Document item 9 separately: Any item 9 above 0 requires documenting a suicide risk reassessment regardless of the total. Document the response, bedside follow-up question, patient's thoughts, plan, intent, means, and actions taken (safety plan, sitter, environmental precautions, provider notification, behavioral health consult, 988 referral if outpatient). 988lifeline.org
- Document the functional impairment response: Ask the functional impairment question (sometimes called item 10) and document the response: not difficult at all, somewhat difficult, very difficult, or extremely difficult. Although this response does not contribute to the total, it is necessary for complete documentation.
- Notify the provider when the score is 10 or higher or item 9 is positive: A total at or above 10 or any positive item 9 should prompt provider notification with the score, severity band, item 9 status, functional impairment, and the action taken so far. Include the score in your next SBAR (Situation, Background, Assessment, Recommendation) handoff, and reassess as often as the patient's clinical trajectory requires.
Frequently Asked Questions
- Is the PHQ-9 a diagnostic tool?
- No, the PHQ-9 serves as a screening tool, not a diagnostic one. A score of 10 or higher suggests possible major depressive disorder but does not confirm the diagnosis. The subsequent clinical interview (performed by a provider or clinician, not the nurse) establishes the diagnosis. Document the score and severity band, not the diagnosis.
- What does a positive item 9 trigger?
- Any item 9 score above 0 ("several days," "more than half the days," or "nearly every day" of thoughts of self-harm) triggers a documented suicide risk reassessment, regardless of the total score. The chart entry must include the patient's response, the bedside follow-up question, their thoughts, plan, intent, means, and the resulting safety plan or escalation. National Patient Safety Goal 15.01.01 (the Joint Commission's standard for suicide risk reduction) requires this documentation in Joint Commission accredited behavioral health care settings.
- How does PHQ-9 differ from PHQ-2?
- PHQ-2 includes the first two items of the PHQ-9 (anhedonia and depressed mood) and serves as an ultra-brief entry screen. A PHQ-2 score of 3 or higher prompts escalation to the full PHQ-9 in primary care. Both tools have comparable sensitivity, but PHQ-9 offers substantially higher specificity. This difference is why a positive PHQ-2 leads to the full PHQ-9 instead of being treated as the final answer.
- Can a nurse administer PHQ-9 independently?
- Yes, a nurse can administer the PHQ-9 independently. It is a self-report instrument and is routinely administered by nursing staff in admission, primary-care, and emergency department settings. The score and the documentation belong to the nurse who administered it; the diagnostic interpretation belongs to a clinician licensed to make a depression diagnosis. Administering and scoring PHQ-9 is within nursing scope; diagnosing major depression from the score is not.
- Is PHQ-9 validated for adolescents?
- No, the adult PHQ-9 is validated for individuals aged 18 and older. For pediatric populations, use the PHQ-A, which adapts the language for adolescents and includes two additional items: irritability and a different phrasing for suicidality. Administering the adult PHQ-9 to a minor may yield a score that does not align with the validated thresholds for that age group.
- How often should PHQ-9 be repeated?
- In primary care, clinicians typically repeat the PHQ-9 every 4 to 6 weeks to monitor treatment response. In inpatient settings, the timing depends on clinical changes; readminister the assessment when symptoms shift or when item 9 is positive, indicating the need to reassess the safety plan. Document the rationale for readministration in the chart to ensure the next reader understands why the score was repeated.
Get the free Nursing Charting Cheat Sheet
- All 16 charting categories, clinical and psych, with what to write for each
- Morse, Braden, Glasgow Coma Scale and SBAR at a glance
- The charting mistakes that cost nurses their licenses
Chart faster with Nurse Charting Pro
Tap through your assessments during the shift and get a draft of your note to review at clock-out. Your notes are cleared from your phone at the end of your shift.
Related Guides
- mental and emotional status chartingMental and Emotional Status category. PHQ-9 is in NCP once the structured field ships. Read this guide for the framework that holds depression, anxiety, and mood observations together.
- safety assessment chartingThe bridge guide for item 9 positive responses. The safety follow-up entry that any positive item 9 produces is documented in the safety assessment category.
- GAD-7 documentationThe paired anxiety screen. PHQ-9 and GAD-7 ride together in primary care because depression and anxiety are highly comorbid. Read the GAD-7 guide if the patient endorses worry, restlessness, or irritability.
- SBAR for psychiatric nursingPHQ-9 should appear in the Background section of any psych SBAR. Score, severity band, item 9 status, and the response action are the four elements that transfer during the handoff.
- psychiatric nursing charting overviewPsychiatric charting overview. PHQ-9 is one of several validated instruments the psych framework uses.