By Amy Niemas, RN-BC, BSN, MSW, Clinical Content Director · Psychiatric Registered Nurse
Last updated: October 13, 2026
How to Score and Document the Barthel Index (Nursing Guide)
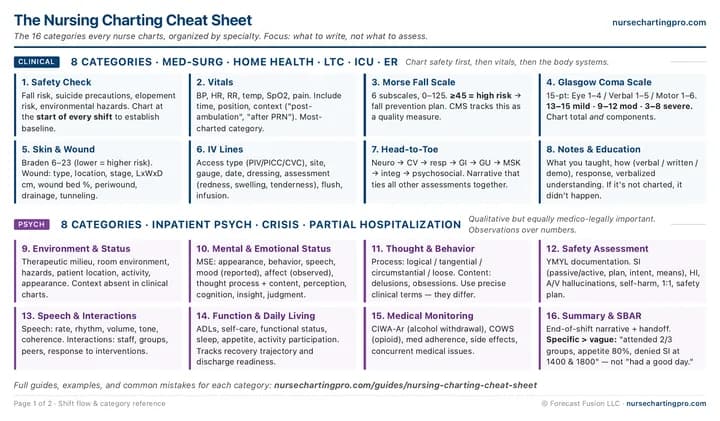
Get the free Nursing Charting Cheat Sheet
- All 16 charting categories, clinical and psych, with what to write for each
- Morse, Braden, Glasgow Coma Scale and SBAR at a glance
- The charting mistakes that cost nurses their licenses
Why This Matters
Regulatory bodies: Centers for Medicare & Medicaid Services (CMS) - Section GG Functional Abilities and Goals, CMS Minimum Data Set (MDS) 3.0 - Skilled Nursing Facility Quality Reporting, CMS OASIS - Home Health Quality Reporting
- Functional evaluation: the Barthel Index — Mahoney FI, Barthel DW. Md State Med J. 1965;14:61-65 (1965)
- Improving the sensitivity of the Barthel Index for stroke rehabilitation — Shah S, Vanclay F, Cooper B. J Clin Epidemiol. 1989;42(8):703-709 (1989)
- The Barthel ADL Index: a reliability study — Collin C, Wade DT, Davies S, Horne V. Int Disabil Stud. 1988;10(2):61-63 (1988)
- Barthel Index - psychometrics, populations, and scoring reference — Shirley Ryan AbilityLab, Rehabilitation Measures Database (2024)
- Barthel Index (BI) - versions and Shah 5-level scoring — Strokengine, Canadian Partnership for Stroke Recovery (2024)
- Barthel Index for Activities of Daily Living (ADL) - online calculator — MDCalc (2026)
- MDS Section G: Functional Status replaced with Section GG: Functional Abilities and Goals — CMS QIES Technical Support Office (2023)
What the Barthel Index Measures and When to Use It
The 10 Barthel Items and Their Point Values
The original Barthel Index scores each item in 5-point increments: 0, 5, 10, or 15, depending on the item. A middle score indicates that the patient needed some assistance but completed more than half the work themselves.
Feeding (0, 5, or 10)
Bathing (0 or 5)
Grooming (0 or 5)
Dressing (0, 5, or 10)
Bowel Control (0, 5, or 10)
Bladder Control (0, 5, or 10)
Toilet Use (0, 5, or 10)
Transfers, Bed to Chair and Back (0, 5, 10, or 15)
Mobility on Level Surfaces (0, 5, 10, or 15)
Stairs (0, 5, or 10)
The 5-point Modified Barthel Index (Shah version)
How to Score at the Bedside
How to Document a Barthel Index Score
The Barthel Index and CMS Section GG (when applicable)
ADL Documentation in NurseChartingPro
Common Mistakes
Scoring What the Patient Could Do Instead of What They Did
The Barthel Index scores actual performance over the preceding 24 to 48 hours, not capacity. Claims like "is able to" reflect capacity rather than actual events. If the patient did not walk unassisted during this time, the independent score overstates function, inflates the total, and can create a discharge plan the patient cannot meet.
Charting Only the Total Score
Two patients with the same total score can have very different issues. A score of 55 based on intact continence and poor mobility requires a different care plan than a 55 based on independent ambulation with incontinence. The item scores provide clinically useful information; the total serves only as a summary.
Counting Supervised Performance as Independent
Supervision is a scoring criterion, not a footnote. If someone must be present for the task to occur safely, the patient is not independent for that item. Scoring it as independent conceals a genuine safety dependency from the next reader and the discharge planner, as well as creates a potentially unsafe situation for the patient.
Charting a Total Without Naming the Version
An 18 indicates near-independence on the Collin 0 to 20 scale, but reflects profound dependence on the 0 to 100 scale. The same score can describe two patients requiring completely different levels of care. Always name the version and include the denominator when your facility uses the 0 to 20 form.
Substituting a Barthel Score for Section GG Items (if applicable)
Section GG items have specific task definitions and a unique helper-effort rating scale. CMS mandates their use during post-acute assessment windows. Do not copy a Barthel score into GG items. Maintain the integrity of both instruments by charting each under its respective name.
Case Example
Scenario
You are the day nurse on an inpatient rehab unit. Mr. Delgado is 10 days out from a right MCA stroke with residual left-sided weakness. His admission Barthel Index was 35. The interdisciplinary care conference meets tomorrow to set his discharge plan, and the weekly Barthel assessment is due on your shift. This morning the aide provided standby supervision while he showered. He fed himself at breakfast and brushed his teeth and shaved himself. He dressed himself except for his left shoe and sock, and in PT he walked the hallway (50 yards) with a rolling walker and one person assisting (other scores/reports are included below).
Chart Entry
1400 Barthel Index (original 0-100 version), scored from this shift and the prior 24 hours based on direct observation, CNA report, and PT note:

Feeding 5 (feeds self; meat cut for him at breakfast and lunch)
Bathing 0 (showered self with standby supervision)
Grooming 5 (brushed teeth and shaved with an electric razor independently)
Dressing 5 (dressed self except for left shoe and sock; more than half of the task self-performed)
Bowel control 10 (continent for 72 hours)
Bladder control 5 (one urinary accident overnight per CNA report)
Toilet use 5 (needs help with clothing management; wipes and flushes self)
Transfers 10 (moved from bed to standing in front of walker with some assistance, holding arm while getting up from bed, and verbal cues)
Mobility 10 (walked 50 yards in the hallway with a rolling walker and assist of one, PT at 1000)
Stairs 0 (not yet attempted per PT)

Total 55, up from 35 on admission (remains in severe dependence band, trending toward moderate). Largest gains in transfers and ambulation. Plan: continue assist of one for toileting and transfers, toileting schedule overnight for bladder accidents, stairs training per PT this week. Will present trend at care conference.
Key points from above chart entry
- Version and evidence sources named up front:
- The entry names the original 0-100 version and the scoring sources (observation, CNA report, PT note), so any reader can reproduce the score. Collin's reliability work is what makes those secondhand sources legitimate.
- Every item score carries its evidence:
- Each parenthetical states what was observed, not just the number. "Walked the hallway for 50 yards with a rolling walker and one person assisting" is much more detailed than the score by itself. Think of the difference between that and just charting "mobility 10".
- Supervision scored as dependent:
- Bathing scores 0 even though Mr. Delgado washed himself, as standby supervision was required.
- Trend and band, not just a total:
- The comparison to admission (35 to 55) and the band label (trending from severe to moderate) turn a number into a recovery trajectory the care conference can act on.
- The score ends in a plan:
- Assist levels, the overnight toileting schedule, and future stairs training all derive from specific item scores. These scores guide the next steps in intervention and care planning.
Pro Tips
- Score each item from the published definitions, not from memory: Keep the printed scoring sheet or the official calculator in front of you. Match the patient's actions to the exact wording of each level. Paraphrased scoring can drift between raters, and the week-over-week trend holds meaning only if every rater scores against the same definitions.
- Use the last 24 hours as your evidence window: You did not watch this patient bathe, dress, and toilet today, and you did not have to. Ask the aide who provided morning care, read the therapy note, ask other providers/staff members, and ask the patient and family. Research on reliability shows that these sources align with direct observation. The evidence window excludes scoring based on memory from last week or "drive-by" hallway impressions.
- The middle score hinges on who does more than half the work: A middle score indicates that the patient needed assistance but still completed most of the task. If the helper performed the majority of the work, lower the score. If the patient did more than the helper, increase the score. Asking "Who did more than half?" out loud clarifies nearly every borderline decision, and the aide can answer this question precisely.
- Name the version each time you chart a total: Original 0-100, Modified (Shah) 5-level, or Collin 0-20. The same patient can score 55 on the 0-100 scale and 11 on the 0-20 scale on the same day. Not writing which version is used leads to significant misinterpretation. If your facility uses the 0-20 version, write the denominator into the entry: 18/20 is much less likely to be misread than just an unnamed 18.
- A score of 100 does not mean the patient can live alone: The Barthel Index focuses solely on basic self-care and mobility. It does not address cooking, medication management, finances, driving, cognition, or judgment. Document a perfect score when the patient achieves it, and ensure the discharge-readiness conversation includes instrumental ADLs and the cognitive aspects that the Barthel Index does not evaluate.
Step by Step
- Confirm the version your facility uses: Original 0-100, Modified (Shah) 5-level, or Collin 0-20. Write the version into your entry before you score anything; the totals are not interchangeable.
- Set the evidence window: Gather information from the past 24 to 48 hours, including your observations, the aide's report from morning care, therapy notes, and feedback from the patient and family.
- Score all 10 items from the published definitions: Match the observed performance to the exact wording of each level. Use the two tie-breakers: supervision indicates the patient is not independent, and assign the middle score to the patient who completed more than half the work.
- Total the score and identify the band: Sum the 10 items. On the 0 to 100 scale: 0-20 total dependence, 21-60 severe dependence, 61-90 moderate dependence, 91-99 slight dependence, 100 total independence.
- Chart the itemized entry with trend and plan: Chart the version, all 10 item scores with their evidence, the total, the change from the prior score, and the subsequent care-plan actions.
Frequently Asked Questions
- What is the Barthel Index?
- The Barthel Index measures independence in 10 basic activities of daily living: feeding, bathing, grooming, dressing, bowel control, bladder control, toilet use, transfers, mobility, and stairs. Mahoney and Barthel developed this index in 1965, and it remains one of the most studied functional measures in stroke and geriatric rehabilitation. The original version scores from 0 to 100, with higher scores indicating greater independence.
- What is the 5-point Barthel Index?
- The 5-point Barthel Index usually refers to the Modified Barthel Index published by Shah, Vanclay, and Cooper in 1989. It keeps the original 10 items but rates each on 5 levels, from unable to perform the task through fully independent, with weighted point values that keep the total on the 0 to 100 scale. The finer steps make it more sensitive to the small functional gains that matter in stroke rehabilitation.
- What Barthel Index score indicates independence?
- On the 0 to 100 scale, a score of 100 indicates independence in all 10 items. The commonly used bands are 0-20 for total dependence, 21-60 for severe dependence, 61-90 for moderate dependence, and 91-99 for slight dependence. In the Collin version, the maximum score is 20. A perfect score reflects independence in basic self-care and mobility only. The index does not assess cooking, medications, finances, or cognition, so it cannot determine if a patient is safe to live alone.
- Is the Barthel Index required by CMS?
- No, the Centers for Medicare & Medicaid Services (CMS) does not require the Barthel Index. In CMS-regulated post-acute settings, Section GG: Functional Abilities and Goals is the required functional documentation. This section replaced Minimum Data Set (MDS) Section G effective October 1, 2023, and appears across skilled nursing, inpatient rehab, long-term care hospital, and home health assessments. The Barthel Index serves as a supplementary clinical tool. Facilities and stroke programs may still use it for trend tracking, and it remains standard in research and in many countries outside the United States.
- Who can score the Barthel Index?
- Nurses, therapists, and physicians can all score the Barthel Index; no licensure restrictions apply. The 1988 Collin reliability study found that patient self-reports, nurses who worked with the patient during a shift, and trained observers produced closely agreeing scores. Your facility policy determines who documents the official score. Anyone scoring it should refer to the published item definitions and the patient's actual performance within the last 24 to 48 hours.
Get the free Nursing Charting Cheat Sheet
- All 16 charting categories, clinical and psych, with what to write for each
- Morse, Braden, Glasgow Coma Scale and SBAR at a glance
- The charting mistakes that cost nurses their licenses
Chart faster with Nurse Charting Pro
Tap through your assessments during the shift and get a draft of your note to review at clock-out. Your notes are cleared from your phone at the end of your shift.
Related Guides
- Morse fall scale scoring and chartingThe other scored assessment charted on nearly every post-acute and long-term care patient. Low Barthel mobility and transfer scores usually pair with a high Morse score.
- Braden scale scoring and wound documentationThe Braden Scale is a similarly scored tool, featuring ordinal subscales, a total score, and a corresponding intervention plan. Patients with low Barthel mobility scores often have Braden scores that indicate a need for pressure-injury prevention.
- Head-to-toe assessment documentationChart the transfer, ambulation, and self-care observations that contribute to the Barthel score each shift.
- The SBAR handoff frameworkInclude the Barthel trend and current assist levels in the Background and Assessment sections of any rehab or post-acute SBAR.
- Clinical nursing charting overviewThis hub guide connects every clinical charting category, including vitals and functional assessments.