Video coming soon — subscribe to be notified when new episodes drop.
Why This Matters
Regulatory bodies: CMS Conditions of Participation (42 CFR 482.24), Joint Commission Pain Assessment and Management Standards (PC.01.02.07)
Federal hospital rules require the medical record to "support the diagnosis, and describe the patient's progress and response to medications and services," with every entry "legible, complete, dated, timed, and authenticated." A conclusion such as "patient comfortable" does not describe anything a reviewer can check; however, a pain rating in the patient's words, along with what you observed, does. For pain, the Joint Commission requires hospitals to reassess and respond to the patient's pain, including "evaluation and documentation of response(s) to pain intervention(s)," which means charting what the patient reports and what you see after your interventions.
Nurses often hear, "If it was not charted, it was not done." The Nurses Service Organization (NSO), a malpractice insurer for nurses, calls that adage "a mistaken belief," but it still lists "pertinent nursing observations" and "patient complaints or concerns" among what the chart should contain. A record that keeps the patient's words and your observations separate, and says who reported what, is easier to rely on months or years later.
How you attribute the patient's words matters too. In a study of 9,251 physician notes at one academic practice, notes about Black patients had higher odds of containing judgment words such as "claims" and "insists." In addition, quoting the patient directly, to record what they said, also helps reduce bias. Also, using words like "states" or "reports" is less judgmental and more clear. This guide covers documentation. It is general information, not legal advice.
Objective data is anything you can observe through hearing, sight, smell, and touch, or measure with a tool. Another nurse could get the same result. Subjective data is what the patient, or another observer, tells you.
Objective Data Examples
- Vital signs: BP 142/86, HR 94, RR 20, SpO2 92% on 2 L nasal cannula
- Breath sounds: crackles in both lung bases
- Skin: warm and dry, raised red rash on the upper back and chest
- Edema: 2+ pitting edema in both ankles
- Wound: 3 cm x 2 cm, pink wound bed, small amount of serous drainage
- Intake and output: 350 mL clear yellow urine since 0600
- Emesis you saw: 300 mL of green emesis at 1015
- Behavior you saw: grimacing and guarding the right lower abdomen when turning
- Height, weight, lab results, and scores such as the Glasgow Coma Scale
Subjective Data Examples
- Pain rating and description: "It is a 7, sharp, and it goes down my right leg."
- Nausea: "I feel sick to my stomach."
- Itching: "I feel itchy all over."
- Dizziness, fatigue, or shortness of breath the patient describes
- Mood in the patient's words: "I feel hopeless."
- Sleep: "I slept maybe two hours last night."
- Some health history the patient gives you, such as overall sense of well-being
- Anything a family member or other individual reports: "Per daughter, patient has been more confused since Tuesday."
Tricky Cases: The Same Finding From Two Sources
Many findings can be either objective or subjective. The question is not what the finding is, but how you learned it.
- Pain: the patient's pain rating is subjective. Grimacing, guarding, and frowning are objective signs you observed. Chart both. Pain behaviors are not always accurate reflections of pain intensity, so the behavior supports the report, but does not replace it. This is particularly an issue in patients with chronic pain, who may appear to be calm or with less pain than they actually have, because they have learned behaviors to compensate.
- Vomiting: emesis you saw and measured is objective. "Per wife, vomited twice at home this morning" is subjective.
- Crying: tears you see are objective. "I have been crying all week" is subjective.
- Anxiety: "I feel anxious" is subjective. Pacing, rapid speech, increased heart rate or blood pressure, and wringing hands are objective. "Patient is anxious" is neither; it is a conclusion, so chart what it is based on (objective, subjective, or both).
- Information from the chart or another nurse: this is secondary data, which may be subjective or objective. Name the source, such as "per ED note" or "per night shift report," and chart your own recheck as objective.
How to Chart Subjective Data
Put the patient's words in quotation marks and say who said them: The patient reports, "..." or The patient's wife states, "..." If the information comes from someone other than the patient, chart who said it.
Quote whole statements, not single words. A single word in quotation marks, or a verb like "claims" or "insists," can read as doubt. Use "states" or "reports" instead, as this is non-biased and direct. Record what the patient said and what you observed. This paints a clear picture of what is going on.
Charting example: Patient reports, "My chest feels tight when I walk to the bathroom." Rates it 4/10. States it goes away after resting for a few minutes. Vital signs WDL. Will alert provider if symptoms worsen or persist.
For mood on a psych unit, the same rule applies: chart the patient's own description in quotation marks. The mental status exam guide shows how that fits with the rest of the assessment.
How to Chart Objective Data
Chart the finding itself, with a number or a description another nurse could check. Where your facility has a structured field for it, such as vital signs, intake and output, or a scored scale, use the field.
Watch for conclusions that look like findings. "Appears comfortable," "tolerated well," and "no apparent distress" tell the next reader what you concluded, not what you saw. Replace them with the observations:
- Chart the findings: "Resting in bed, eyes closed, respirations even and unlabored at 16. Rates pain 2/10 when awake." versus "Appears comfortable."
- Chart the findings: "Walked 50 feet with rolling walker, steady gait, SpO2 95% on room air after walking, denies dizziness." versus "Tolerated ambulation well."
- Chart the findings: "Speaking in full sentences, no accessory muscle use, RR 18." versus "No apparent distress."
For patients who cannot rate their own pain, behavioral scales such as the FLACC scale turn observed behavior into a score. The score is objective data. It is not the same as a pain intensity rating from the patient.
Putting Them Together in a Note
Most nursing notes pair a symptom the patient reports with the sign you observed. Chart them side by side, with the source of each clear.
Charting example: Patient reports, "I feel itchy all over." Raised red rash on the upper back and chest observed. Skin warm and dry. Provider notified at 1030.
Formats that separate the two, such as SOAP (subjective, objective, assessment, plan), put the patient's report under S and your findings under O. Whatever format your facility uses, the rule is the same: the reader should be able to tell what the patient said from what you observed. The summary narrative guide covers how to bring both into an end-of-shift note, and the SBAR handoff framework shows where each goes when you give report.
Objective and Subjective Data on a Care Plan
In the nursing process, assessment comes first, and it includes both kinds of data. On a care plan, the assessment section lists the subjective data (what the patient reports) and the objective data (what you observed and measured) that support the nursing diagnosis.
Charting example for a care plan: Subjective: patient states, "I get short of breath when I walk to the bathroom." Objective: RR 24 and SpO2 89% on room air after walking 20 feet, returned to 94% after 3 minutes of rest.
Objective and Subjective Data in NurseChartingPro
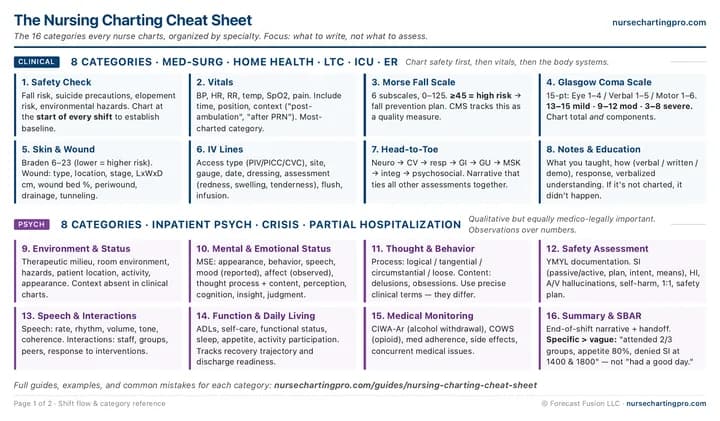
In NurseChartingPro, most of what you select in the clinical categories is objective data: vital signs, head-to-toe findings, and scores. The psych categories combine observed behavior with notes fields, and Speech and Interactions has a Notable Quotes field for the patient's direct statements. When you add a patient or other person's report in a notes field, put it in quotation marks and indicate who said it. The clinical nursing charting overview and the psychiatric nursing charting overview walk through each category.
Common Mistakes
Charting a conclusion as a finding
❌Weak: Patient is depressed.
✅Strong: Patient states, "I have not wanted to get out of bed for a week." Stayed in bed today until 1100, declined breakfast and only made minimal eye contact during assessment.
"Depressed" is a conclusion. The strong version gives the patient's words and what you observed, which is what the conclusion would rest on.
Charting a patient report as if you observed it
❌Weak: Patient vomited twice this morning.
✅Strong: Per wife, patient vomited twice at home this morning. No emesis observed since arrival at 0900.
The weak version reads as if you saw it. When someone else reports a finding, chart who reported it, and chart what you have observed yourself.
Using a behavior in place of the pain rating
❌Weak: Patient grimacing, pain 8/10.
✅Strong: Patient rates pain 8/10 and states, "It is sharp in my right side." Grimacing and guarding right lower abdomen when turning.
The pain rating comes from the patient. The grimace is your observation. Keep them separate so the next nurse knows which part the patient reported.
Charting a vague word instead of what you saw
❌Weak: Appears comfortable.
✅Strong: Resting in bed, eyes closed, respirations even and unlabored at 16. Rates pain 2/10 when awake.
"Appears comfortable" is a conclusion without a finding behind it. Chart the findings that led you there.
Quoting a patient in a way that signals doubt
❌Weak: Patient claims pain is "8."
✅Strong: Patient reports pain 8/10, "sharp, worse when I cough."
Words such as "claims" and a single number in quotation marks suggest you doubt the patient. Report what the patient said and chart what you observed alongside it.
Pro Tips
💡
Ask yourself how you know it: If you saw, heard, smelled, felt, or measured it, it is objective. If someone told you, it is subjective, and the chart should say who told you.
💡
Pair the symptom with the sign: When a patient reports a symptom, look for a sign that goes with it and chart both. "Reports itching" plus "raised red rash on the upper back" tells the provider far more than either one alone.
💡
Quote the patient when the words matter: Pain descriptions, mood, safety statements, and anything the patient says about their own care are worth quoting. A quote takes the same space as a paraphrase, keeps the patient's meaning, and typically carries more weight than paraphrasing.
💡
Reread for words like appears and seems: They are not wrong, but they often stand in for a finding you could name. If you wrote "appears," add what you saw. Example: "Appears depressed." versus "Presents with flat affect, minimal eye contact, and poor hygiene. Also sleeping in bed until 1 p.m., refused breakfast, and only ate bites at lunch."
Step by Step
Ask how you know it: Decide whether you observed or measured the finding, or whether someone told you about it.
Chart objective data as the finding: Record the number or a description another nurse could check, in a structured field if your facility has one.
Chart subjective data in the patient's (or other person's) words: Put the statement in quotation marks if at all possible and say who said it.
Name secondary sources: For information from family, the chart, another nurse, or provider, name the source.
Pair symptoms with signs: Chart the patient's report along with what you observed, so the reader can tell them apart.
Frequently Asked Questions
What is the difference between objective and subjective data in nursing?
Objective data is what you observe or measure, such as vital signs, breath sounds, a rash, or a wound measurement. Subjective data is what the patient or another person tells you, such as a pain rating, nausea, or how they slept.
Is pain objective or subjective?
Pain is subjective: the patient's report is the rating. Signs such as grimacing and guarding are objective observations that support the report but do not replace it.
Is a patient frowning objective or subjective?
A patient frowning is objective data, because you observed it. If the patient tells you why they are frowning (e.g., "I'm mad."), that part is subjective.
Is vomiting objective or subjective?
Vomiting you saw is objective, and you can chart the amount and color. Vomiting a patient or other person tells you about is subjective, so chart who reported it.
Is crying objective or subjective?
Crying you see is objective. A patient saying they have been crying is subjective.
Are family reports subjective data?
Yes, family reports are subjective data from a secondary source. Chart who gave the information, such as "per daughter."
What do objective and subjective mean on a care plan?
In the assessment section of a care plan, subjective data is what the patient reports, and objective data is what you observed and measured. Both support the nursing diagnosis.
Get the free Nursing Charting Cheat Sheet
All 16 charting categories, clinical and psych, with what to write for each
Morse, Braden, Glasgow Coma Scale and SBAR at a glance
The charting mistakes that cost nurses their licenses
Tap through your assessments during the shift and get a draft of your note to review at clock-out. Your notes are cleared from your phone at the end of your shift.