By Miranda Niemas, Nursing Student (BSN candidate)
This guide is currently pending review by a licensed registered nurse.
Last updated: October 13, 2026
FLACC Pain Scale: Nursing Guide for Nonverbal Pain Assessment
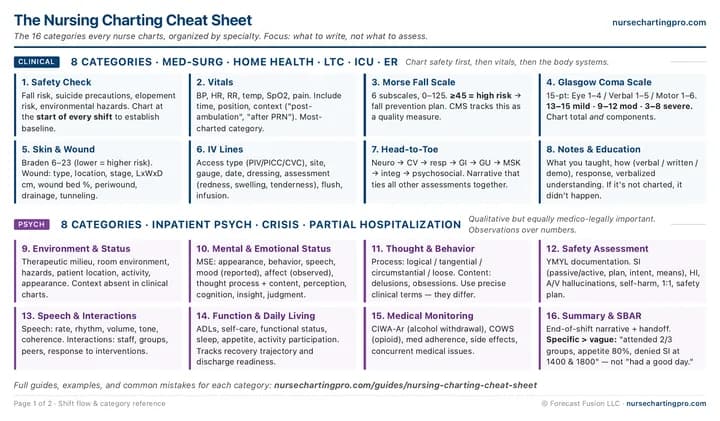
Get the free Nursing Charting Cheat Sheet
- All 16 charting categories, clinical and psych, with what to write for each
- Morse, Braden, Glasgow Coma Scale and SBAR at a glance
- The charting mistakes that cost nurses their licenses
My first FLACC score was wrong because I gave a post-op 4 year old a 2/10 after he told me he was fine. He was nonverbal from emergence delirium, not pain-free, and his legs were drawn up while he whimpered. FLACC is what saves you from a patient who cannot self-report but is clearly not comfortable. This guide breaks down each of the five categories, what each score actually looks like at the bedside, and how to document the result so the next nurse knows what changed.
Why This Matters
Regulatory bodies: American Academy of Pediatrics (AAP) - Pediatric Pain Management, The Joint Commission - Pain Assessment and Management Standards, International Association for the Study of Pain (IASP) - Pain Assessment in Nonverbal Patients, CMS Hospital Conditions of Participation - Pain Management
- The FLACC: a behavioral scale for scoring postoperative pain in young children — Merkel SI, Voepel-Lewis T, Shayevitz JR, Malviya S. Pediatr Nurs. 1997;23(3):293-297 (1997)
- The revised FLACC observational pain tool: improved reliability and validity for pain assessment in children with cognitive impairment — Malviya S, Voepel-Lewis T, Burke C, Merkel S, Tait AR. Paediatr Anaesth. 2006;16(3):258-265 (2006)
- R3 Report Issue 11: Pain Assessment and Management Standards for Hospitals — The Joint Commission (2017)
- Pain Assessment and Treatment in Children With Significant Impairment of the Central Nervous System — American Academy of Pediatrics (AAP) (2017)
What the FLACC pain scale is and when to use it
The five scoring categories
What each score looks like at the bedside, with the specific behaviors that distinguish 0, 1, and 2.
F - Face (0-2)
L - Legs (0-2)
A - Activity (0-2)
C - Cry (0-2)
C - Consolability (0-2)
How nurses document a FLACC score
The score is the easy part. Documenting it in a way that drives clinical action is the part that matters.
FLACC vs CPOT vs BPS and the 0-10 numeric scale
Picking the right tool for your patient is more important than picking one you already know.
Self-report (0-10 numeric or Wong-Baker) first
FLACC for pediatric and cognitively impaired patients
CPOT for adult ICU patients
BPS for intubated adults without facial observation
FLACC in NurseChartingPro
Common Mistakes
Using FLACC on a patient who can self-report
Self-report is the gold standard for pain intensity. Using a behavioral tool on a patient who can speak their pain undercuts the validity of the assessment and creates a score that does not reflect the actual patient experience.
Scoring only the total without the category breakdown
A total of 5 does not tell the next nurse whether the pain presents as global unease (each category at 1) or as two categories at 2 plus a comfortable third. Documenting category scores preserves the clinical picture for reassessment.
Not attempting to console before scoring Consolability
Consolability is the only category that requires an action from the nurse before scoring. Without attempting comfort, the Consolability score is a guess rather than an observation.
Skipping reassessment after the PRN analgesic
Opioid reassessment is both a clinical and a legal requirement. A PRN given without a documented reassessment score is an incomplete pain management record and a common survey finding.
Mixing FLACC with the 0-10 numeric scale in the same entry
FLACC and the 0-10 numeric scale are different instruments with different validation populations. Writing "7/10 (FLACC)" conflates them and makes chart audit and trend tracking harder. The total is on a 0-10 range, but the scale is FLACC, not numeric.
Case Example
Scenario
You are the evening shift nurse. Jordan came out of the PACU at 1600 after a laparoscopic appendectomy. At 1830 you enter the room to do a scheduled pain assessment. Jordan is lying on his right side with knees drawn up. His face is frowning and he whimpers when you pull back the blanket to check the dressing. His mother is at the bedside holding his hand. When you say "hi Jordan, can you tell me how you feel," he turns his face to the wall and does not answer. His IV hydromorphone PCA basal is running; last demand dose was at 1700.
Chart Entry
Pain assessment 1830:

FLACC total: 6
- Face: 2 - frequent frown, jaw clenched when dressing touched
- Legs: 2 - knees drawn up toward abdomen, guarding posture
- Activity: 1 - squirming when repositioned, tense
- Cry: 1 - whimpers with dressing contact, no steady crying
- Consolability: 0 - calmed when mother held hand and I stopped dressing check; responds to maternal presence

Clinical context: nonverbal (turned away when asked); PCA basal running; last bolus 1700.

Intervention: PCA bolus delivered 1832; position changed to right side with knees supported on pillow; mother coached on PCA button technique.

Reassessment at 1900: FLACC 2 (Face 1 - slightly withdrawn but no frown, Legs 0 - extended and relaxed, Activity 1 - shifting position occasionally, not guarding, Cry 0, Consolability 0). Continue scheduled assessment q2h and PRN.
Key points from above chart entry
- Category breakdown documented:
- All five scores listed individually so the next nurse sees the pain presents as Face and Legs, not crying.
- Consolability scored based on actual attempt:
- Mother was already present; the nurse observed the calming response before scoring 0, rather than assuming.
- Intervention + reassessment within 30 minutes:
- PCA bolus at 1832, reassess at 1900 - within the standard 30-minute post-PRN window.
- No numeric self-report attempted:
- Jordan turned away when asked, which is an appropriate trigger to switch from self-report to FLACC. The chart notes the trigger so the tool choice is defensible.
Pro Tips
- Always try self-report first, document why you switched: If a child is old enough to point at Wong-Baker faces or speak a number, try that before FLACC. When you switch to FLACC, write one line in the chart about why (nonverbal, emergence delirium, sedated, cognitively impaired). This protects the score from an audit question about tool choice.
- Observe for the full rated period: The original FLACC protocol specifies a 1 to 5 minute observation window. A 10-second glance at a sleeping child is not a FLACC. Build the observation into the standard pain assessment rather than trying to score on the fly.
- Compare Face to a baseline photo or parent description: A furrowed brow can be pain or can be the child's resting face. If there is a baseline admission photo, check it. If there is not, ask the parent "does he always look like that when he is comfortable." A two-sentence parent quote in the chart strengthens the score.
- Score Consolability after, not before, a comfort attempt: Walking in, watching for 15 seconds, and scoring 0 on Consolability is a guess. Try positioning, caregiver presence, or talking to the patient, then score based on the response. This single habit changes FLACC accuracy more than any other.
- Pair every opioid FLACC with a reassessment within 30 minutes: The reassessment score is what closes the clinical and legal loop. Document the intervention time, the reassessment time, and the new FLACC. A PRN opioid without a documented reassessment score is a survey finding waiting to happen.
Step by Step
- Confirm FLACC is the right tool for this patient: If the patient can self-report pain reliably via the numeric scale or Wong-Baker faces, use that instead. If the patient is nonverbal, sedated, or cognitively impaired, FLACC is appropriate.
- Observe the patient for 1 to 5 minutes: Watch the patient without intervening. Note facial expression, leg position, body activity, and whether the patient is crying or vocalizing.
- Score each of the five categories 0 to 2: Face, Legs, Activity, Cry, and Consolability each get a 0, 1, or 2 based on the published rubric. Consolability requires a comfort attempt before scoring.
- Sum the categories for a total of 0 to 10: Total 0 = relaxed, 1-3 = mild discomfort, 4-6 = moderate pain, 7-10 = severe pain.
- Intervene and reassess: For scores 4 and above, apply a pain intervention, such as an as-needed (PRN) analgesic, a nonpharmacologic measure, or provider notification. Reassess the FLACC within the window appropriate to the intervention and document the new score.
Frequently Asked Questions
- What does a FLACC score of 4 mean?
- A FLACC score of 4 falls in the moderate pain range (4-6). It means the patient is showing behavioral signs of pain across multiple categories and should prompt a review of scheduled and as-needed (PRN) pain orders, an intervention if clinically appropriate, and a reassessment within the window your facility sets. A 4 is not a "wait and see" score; it is a score that should drive a decision.
- Is FLACC only for pediatric patients?
- No, FLACC is not only for pediatric patients. It was validated for children ages 2 months to 7 years; the revised FLACC (r-FLACC) was validated for children with cognitive impairment and is widely applied to cognitively impaired adults and other nonverbal adults, such as those with advanced dementia or emerging from anesthesia. For adult intensive care unit (ICU) patients, the Critical-Care Pain Observation Tool (CPOT) and the Behavioral Pain Scale (BPS) are the usual choices, not FLACC; check your facility policy for which behavioral scale it prefers.
- How is FLACC different from the numeric 0-10 pain scale?
- FLACC is an observational tool, while the numeric 0-10 pain scale is a self-report tool. With the numeric scale, the patient states their pain intensity; with FLACC, the nurse rates five behavioral categories the patient displays. Both produce a score on a 0-10 range, but they are measuring different things. Self-report is preferred when the patient can reliably speak or point; FLACC is a fallback for patients who cannot self-report. You should not use both tools on the same patient at the same time or mix their scores in a single chart entry.
- Do I need to document all five FLACC category scores, or only the total?
- Best practice is to document all five category scores plus the total. A total of 5 with one category at 2 looks very different clinically from a total of 5 with five categories at 1 each, and the next nurse needs the breakdown to know what to watch for. Many facilities require the category-level documentation; check your charting policy. In NurseChartingPro, the total enters the structured field and the category-level detail can be added in the notes section of the pain assessment.
- How often should I reassess with FLACC after giving a pain medication?
- Reassessment timing follows the medication and your facility policy, not the FLACC tool itself. After an IV opioid, reassess within 15 to 30 minutes. After an oral analgesic, reassess within 45 to 60 minutes. After a scheduled non-opioid like acetaminophen, reassess at the next standard interval. Document the reassessment FLACC with the time; an intervention without a reassessment score is an incomplete pain management record.
Get the free Nursing Charting Cheat Sheet
- All 16 charting categories, clinical and psych, with what to write for each
- Morse, Braden, Glasgow Coma Scale and SBAR at a glance
- The charting mistakes that cost nurses their licenses
Chart faster with Nurse Charting Pro
Tap through your assessments during the shift and get a draft of your note to review at clock-out. Your notes are cleared from your phone at the end of your shift.
Related Guides
- BPS pain scale documentationThe behavioral pain tool for intubated, sedated adult ICU patients. 3 items on a 3 to 12 range. FLACC is for pediatric and cognitively impaired patients; BPS is the adult ICU sibling.
- CPOT pain scale documentationThe behavioral pain tool for non-self-reporting adult ICU patients (intubated or extubated). 4 items on a 0 to 8 range. FLACC and CPOT cover different populations; the trigger-and-response documentation rhythm is the same.
- PAINAD pain scale for advanced dementiaThe behavioral pain tool for non-verbal patients with advanced dementia in med-surg, long-term care, and memory care. 5 items on a 0 to 10 range, with a 5-minute observation window built into the protocol.
- Skin & Wound charting (pain block)FLACC is selectable in the pain block of the Skin and Wound assessment in NurseChartingPro alongside BPS, CPOT, and PAINAD; see the full pain-documentation walkthrough.
- Clinical nursing charting hubOverview of all clinical charting categories with pain assessment in context.
- Objective vs subjective data in nursingWhy a behavioral pain score is objective data and a pain rating is subjective.