By Miranda Niemas, Nursing Student (BSN candidate)
This guide is currently pending review by a licensed registered nurse.
Last updated: October 13, 2026
PAINAD Pain Scale: Nursing Guide for Non-Verbal Patients with Advanced Dementia
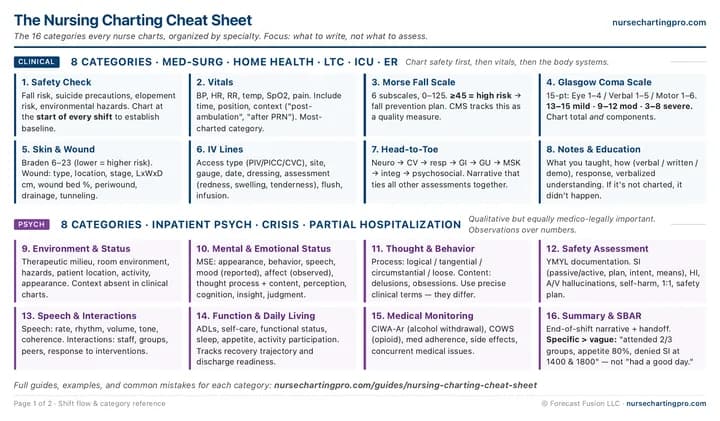
Get the free Nursing Charting Cheat Sheet
- All 16 charting categories, clinical and psych, with what to write for each
- Morse, Braden, Glasgow Coma Scale and SBAR at a glance
- The charting mistakes that cost nurses their licenses
Your med-surg patient is an 84 year old admitted for hip fracture, advanced dementia, nonverbal at baseline. Day shift charted "denies pain" with a numeric 0/10. By 1400 the patient is grimacing, moaning intermittently, and pulling away when you try to reposition. I had a similar handoff during my med-surg rotation last semester and could not have told you on the spot which behavioral tool to use, because the FLACC chip was not on this unit. This guide breaks down each of the 5 PAINAD items, what the scores look like at the bedside, why a numeric 0/10 self-report on a nonverbal dementia patient is a documentation problem, and what a defensible PAINAD chart entry includes.
Why This Matters
Regulatory bodies: American Geriatrics Society (AGS) - Persistent Pain in Older Persons, Centers for Medicare & Medicaid Services (CMS) - Long-Term Care Pain Management, The Joint Commission - Pain Assessment and Management Standards, Alzheimer's Association - Behavioral Pain Indicators in Dementia
- Development and psychometric evaluation of the Pain Assessment in Advanced Dementia (PAINAD) scale — Warden V, Hurley AC, Volicer L. J Am Med Dir Assoc. 2003;4(1):9-15 (2003)
- Pain assessment for people with dementia: a systematic review of systematic reviews of pain assessment tools — Lichtner V, Dowding D, Esterhuizen P, et al. BMC Geriatr. 2014;14:138 (2014)
- Pain in non-communicative older adults beyond dementia: a narrative review — Tagliafico L, Maizza G, Ottaviani S, et al. Front Med (Lausanne). 2024;11:1393367 (2024)
- R3 Report Issue 11: Pain Assessment and Management Standards for Hospitals — The Joint Commission (2017)
What PAINAD is and when to use it
The 5 PAINAD items
What each item scores at the bedside, with the specific behaviors that distinguish 0, 1, and 2.
Item 1 - Breathing (independent of vocalization, 0 to 2)
Item 2 - Negative vocalization (0 to 2)
Item 3 - Facial expression (0 to 2)
Item 4 - Body language (0 to 2)
Item 5 - Consolability (0 to 2)
Charting the total and the items
How nurses document a PAINAD score
The score is the easy part. Documenting it in a way that drives intervention and differentiates pain from agitation is the part that matters.
PAINAD vs FLACC vs BPS vs CPOT and the 0 to 10 numeric scale
Picking the right tool for your patient is more important than picking one you already know.
Self-report (0 to 10 numeric or Wong-Baker faces) first
PAINAD for non-verbal patients with advanced dementia
FLACC for pediatric and cognitively impaired patients across age ranges
BPS for intubated, sedated adult ICU patients
CPOT for non-self-reporting adult ICU patients (intubated or extubated)
PAINAD in NurseChartingPro
Common Mistakes
Charting "denies pain 0/10" on a nonverbal dementia patient
A 0/10 self-report from a patient who cannot reliably self-report is a documentation problem and a survey finding. The Joint Commission requires a validated tool appropriate to the patient. Switch to PAINAD (or your unit's behavioral tool) and document why.
Scoring without the 5-minute observation window
PAINAD is designed around a 5-minute observation period. A 30-second glance produces a score that does not capture the patient's actual presentation, and pain in dementia often shows up intermittently across a longer window. Build the observation into the assessment time rather than scoring on the fly.
Confusing pain with BPSD agitation
Differentiating pain from BPSD agitation is the central documentation discipline in PAINAD. The way you do it in the chart is by capturing the trigger and the response to analgesia. A score that drops with analgesia is pain; a score that does not respond is more consistent with agitation and warrants a different intervention. Skipping the trial and labeling the patient "behavioral" risks under-treating pain.
Scoring only the total without the item breakdown
A total of 5 does not tell the next nurse whether the pain presents as facial-and-body-language guarding (more consistent with somatic pain) or as vocalization-and-consolability distress (more consistent with global discomfort or BPSD overlap). Documenting the item scores preserves the clinical picture for reassessment and pattern recognition across shifts.
Not attempting to console before scoring Consolability
Consolability is the only item that requires an action from the nurse before scoring. Without attempting comfort, the consolability score is a guess rather than an observation. In dementia, consolability is also a key differentiator of pain from agitation: a patient who calms with a familiar voice may be agitated rather than in pain.
Skipping reassessment after the PRN analgesic
Opioid reassessment is both a clinical and a legal requirement. A PRN given without a documented reassessment score is an incomplete pain management record and a common survey finding. The reassessment also confirms the score reflected pain (responded to analgesia) rather than BPSD agitation.
Case Example
Scenario
You are the day shift med-surg nurse. Mr. Henderson came up from PACU yesterday after right hip ORIF for a femoral neck fracture. He has advanced Alzheimer disease and is nonverbal at baseline; his daughter is at the bedside. Day shift documented "denies pain 0/10" on the previous shift, but Mr. Henderson has scheduled acetaminophen and a PRN morphine 2 mg IV order. At 1400 you walk in for a scheduled assessment as the bedside CNA is about to reposition him. You ask the daughter what his face looks like at home when he is comfortable, then observe for 5 minutes during the turn.
Chart Entry
Pain assessment 1400:

PAINAD total: 6
- Breathing: 0 - regular respirations 18 per minute, no labored effort
- Negative vocalization: 1 - occasional low-level moaning during the turn, no calling out
- Facial expression: 2 - sustained grimace during repositioning per family confirmation that this does not match baseline; baseline face is neutral or smiling per daughter
- Body language: 2 - rigid through the right leg, fists clenched, pulled away from the affected side
- Consolability: 1 - calmed when daughter held his hand and spoke; partial calming, did not fully resolve grimacing

Clinical context: nonverbal at baseline (advanced Alzheimer disease); numeric self-report not appropriate. 5-minute observation during scheduled repositioning. Right hip ORIF POD 1, scheduled acetaminophen 650 mg PO q6h on board, last dose 1100. PRN morphine 2 mg IV available.

Intervention: morphine 2 mg IV delivered at 1405 with daughter present; reposition completed slowly with family-coached reassurance; comfort measures continued through the turn (heated blanket, head of bed elevation maintained at 30 degrees).

Reassessment at 1430: PAINAD 2 (Breathing 0, Vocalization 0, Facial expression 1 - mild brow lowering at rest, Body language 1 - tense at right leg only, Consolability 0). 5-minute observation at rest after repositioning complete. Pattern consistent with procedural pain (responded to analgesia).

Plan: pre-medicate 30 minutes before next scheduled repositioning with PRN morphine; PAINAD reassess at 1700 and PRN; communicate pre-medication plan to night shift in handoff.
Key points from above chart entry
- Numeric 0/10 self-report rejected with documentation:
- The chart explicitly states why the numeric scale is not appropriate (nonverbal at baseline, advanced Alzheimer disease) and switches to PAINAD. This protects the score choice at chart audit.
- Item breakdown documented:
- All 5 item scores are listed individually so the next nurse sees the pain presents as facial-and-body-language guarding around the right leg, not as global agitation.
- Family at bedside used as the baseline reference:
- The daughter confirmed that the grimacing face does not match baseline. A two-sentence family quote in the chart strengthens the score and makes the case that this is pain, not BPSD agitation.
- Trigger captured (repositioning), not just rest:
- PAINAD scoring during a known nociceptive trigger (repositioning of a fresh ORIF leg) is more clinically interpretable than scoring at rest. The chart names the trigger so the score is read in context.
- Response-to-analgesia confirms pain vs agitation:
- The score dropped from 6 to 2 within 30 minutes of IV morphine, which is the documentation pattern that distinguishes pain from BPSD agitation. This is the core PAINAD discipline.
- Forward plan includes pre-medication:
- The plan to pre-medicate before the next repositioning is the right downstream decision from a procedural-pain finding. It is documented in the chart for night shift to follow.
Pro Tips
- Use the 5-minute observation window the protocol specifies: The original PAINAD protocol specifies a 5-minute observation period. A 30-second glance produces a score that does not capture the patient's actual presentation, and pain in dementia often shows up intermittently across a longer window. Build the 5 minutes into the assessment time rather than scoring on the fly. Pair the observation with a known trigger (repositioning, dressing change, bathing) when possible.
- Capture the trigger and the response to analgesia: Differentiating pain from BPSD agitation is the central PAINAD discipline. The chart pattern that does it is: trigger documented, score documented, intervention given, reassessment score documented. A score that drops with analgesia is pain. A score that does not respond is more consistent with agitation and should drive a different intervention. Skipping the analgesic trial labels the patient "behavioral" without evidence and risks under-treating real pain.
- Use the family at the bedside as the baseline reference: Family members often know what the patient's comfortable face, comfortable body posture, and baseline vocalizations look like at home. A two-sentence family quote in the chart ("daughter states grimacing face is not baseline; he is normally neutral or smiling at home") strengthens the score and protects it at chart audit. In dementia care, the family is one of the most underused diagnostic resources.
- Pre-medicate around recurring care episodes: When a patient consistently scores high during repositioning, dressing change, or bathing, the right downstream decision is to pre-medicate 30 to 60 minutes before the care episode. Document the pre-medication plan in the chart so night shift and the oncoming nurses follow the same approach. PAINAD is most useful as a feedback loop: the score informs the analgesic plan, and the plan changes the score on the next assessment.
- Score Consolability after, not before, a comfort attempt: Walking in, watching for 15 seconds, and scoring 0 or 2 on Consolability is a guess. Try positioning, familiar voice, family-member presence, or a redirection technique your unit uses for dementia care, then score based on the response. This single habit changes PAINAD accuracy and is a key differentiator of pain from agitation.
Step by Step
- Confirm PAINAD is the right tool for this patient: If the patient with mild or moderate dementia can still point at a Wong-Baker faces card or speak a number reliably, use a self-report tool. If the patient is non-verbal at baseline (advanced dementia, late-stage Alzheimer disease, aphasic stroke) and cannot self-report, PAINAD is appropriate.
- Establish the patient baseline first: Ask family at the bedside or check the admission sheet for the patient's baseline face, baseline vocalization, and baseline body posture. PAINAD scores are interpretable against this baseline; a furrowed brow is meaningful only if the baseline face is neutral.
- Observe the patient for 5 minutes, ideally during a known trigger: Watch the patient before you intervene. Note breathing, vocalization, facial expression, and body language. Pair the observation with a known trigger (repositioning, dressing change, bathing) when clinically possible because procedural pain in dementia is the most common trigger and the most actionable finding.
- Score each of the 5 items 0 to 2: Breathing, negative vocalization, facial expression, body language, and consolability each get a 0, 1, or 2 based on the published rubric. Consolability requires a comfort attempt before scoring.
- Sum the items for a total of 0 to 10: Total 0 = no pain. 1 to 3 = mild pain. 4 to 6 = moderate pain. 7 to 10 = severe pain. Many facilities treat 2 or higher as a documented intervention threshold for nonverbal dementia patients.
- Intervene and reassess: For scores 2 and above (per facility policy), apply a pain intervention, such as an as-needed (PRN) analgesic, a nonpharmacologic measure, or provider notification, and reassess within the window appropriate to the intervention. Document the reassessment PAINAD with the time. The response to analgesia is what differentiates pain from agitation caused by behavioral and psychological symptoms of dementia (BPSD) in the chart.
Frequently Asked Questions
- What does a PAINAD score of 4 mean?
- A PAINAD of 4 falls in the moderate pain range (4 to 6). It means the patient is showing behavioral signs of pain across multiple items and should prompt a review of scheduled and as-needed (PRN) pain orders, an intervention if clinically appropriate, and a reassessment within the window for the medication given. A 4 is not a "wait and see" score; it is a score that should drive a decision and a documented response to analgesia.
- Is PAINAD only for advanced dementia?
- PAINAD is mainly for non-verbal patients with advanced dementia, the group it was developed and validated in. It is most appropriate for patients with late-stage Alzheimer disease, advanced vascular dementia, or aphasic stroke who cannot reliably self-report. For patients with mild or moderate dementia who can still point at a Wong-Baker faces card or speak a number, use a self-report tool first. For pediatric patients, use FLACC (Face, Legs, Activity, Cry, Consolability). For adult patients in the intensive care unit (ICU), use the Behavioral Pain Scale (BPS) or the Critical-Care Pain Observation Tool (CPOT).
- How is PAINAD different from FLACC?
- PAINAD and FLACC (Face, Legs, Activity, Cry, Consolability) both score 5 behavioral items on a 0 to 10 range, and the items overlap (facial expression, body movement, vocalization or cry, consolability). PAINAD substitutes Breathing for the Legs item and uses dementia-specific item language (negative vocalization, striking-out body language). FLACC is validated for pediatric patients and via the revised FLACC for cognitively impaired patients across age ranges. PAINAD is the dementia-specific tool. The choice between them in cognitively impaired adults is usually facility policy.
- How is PAINAD different from the numeric 0 to 10 pain scale?
- The numeric 0 to 10 scale is a self-report tool: the patient states their pain intensity. PAINAD is an observational tool: the nurse rates 5 behavioral items the patient displays during a 5-minute observation. Both produce a score on a 0 to 10 range, but they are measuring different things. Self-report is preferred when the patient can reliably speak or point; PAINAD is the fallback for non-verbal dementia patients. Do not use both tools on the same patient at the same time or mix their scores in a single chart entry.
- How do I tell the difference between pain and BPSD agitation on PAINAD?
- On PAINAD, you tell pain from behavioral and psychological symptoms of dementia (BPSD) agitation by charting the trigger and the response to analgesia. A high PAINAD during a known painful trigger (repositioning of a fracture, dressing change, bathing) that drops within 30 to 60 minutes of an analgesic is consistent with pain. A high PAINAD with no clear trigger that does not respond to analgesia is more consistent with BPSD agitation and warrants a different intervention plan (environmental, redirection, family presence, scheduled medication review). PAINAD has a documented false-positive rate in dementia, so the analgesic trial is part of the documentation discipline.
- How often should I reassess with PAINAD after giving a pain medication?
- Reassessment timing follows the medication and your facility policy, not the PAINAD tool itself. After an IV opioid, reassess within 15 to 30 minutes. After an oral analgesic, reassess within 45 to 60 minutes. After a scheduled non-opioid like acetaminophen, reassess at the next standard interval. Document the reassessment PAINAD with the time and the trigger. An intervention without a reassessment score is an incomplete pain management record and does not differentiate pain from BPSD agitation.
Get the free Nursing Charting Cheat Sheet
- All 16 charting categories, clinical and psych, with what to write for each
- Morse, Braden, Glasgow Coma Scale and SBAR at a glance
- The charting mistakes that cost nurses their licenses
Chart faster with Nurse Charting Pro
Tap through your assessments during the shift and get a draft of your note to review at clock-out. Your notes are cleared from your phone at the end of your shift.
Related Guides
- Clinical nursing chartingThe 8 clinical charting categories, including where pain scores fit in the shift.
- FLACC pain scale documentationThe closest sibling tool. FLACC is for pediatric patients and via the revised FLACC for cognitively impaired patients across age ranges. PAINAD overlaps in the cognitively-impaired-adult population; the choice is usually unit policy.
- BPS pain scale documentationThe behavioral pain tool for intubated, sedated adult ICU patients. PAINAD is for non-verbal dementia patients outside the ICU; if a dementia patient is admitted and intubated, the team typically switches to BPS for the ICU stay.
- CPOT pain scale documentationThe behavioral pain tool for non-self-reporting adult ICU patients (intubated or extubated). Adopt CPOT or BPS for the ICU stay; return to PAINAD on the floor or in long-term care.
- CIWA-Ar DocumentationAnother behavioral scoring tool with the same "score, intervene, reassess" documentation rhythm and the same trigger-and-response discipline.
- COWS DocumentationThe opioid-withdrawal counterpart. Same documentation rhythm and trigger-and-response discipline as the behavioral pain tools.
- Skin and Wound charting (pain block)PAINAD is selectable in the pain block of the Skin and Wound assessment in NurseChartingPro; see the full pain-documentation walkthrough for the structured-field flow.