By Miranda Niemas, Nursing Student (BSN candidate)
This guide is currently pending review by a licensed registered nurse.
Last updated: October 13, 2026
BPS Pain Scale: Nursing Guide for Ventilated Adult ICU Patients
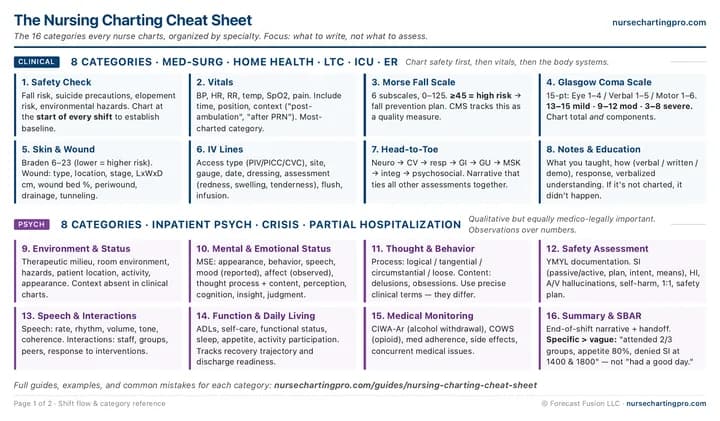
Get the free Nursing Charting Cheat Sheet
- All 16 charting categories, clinical and psych, with what to write for each
- Morse, Braden, Glasgow Coma Scale and SBAR at a glance
- The charting mistakes that cost nurses their licenses
Your post-op patient is on propofol and fentanyl, intubated, RASS -2, and the day shift charted a BPS of 9 at 0700 with no documented response. By the time you walk in, the patient is bucking the vent and the brow is locked. I sat through this exact handoff in my critical-care rotation last semester and could not have told you whether 9 was bad without looking up the threshold. This guide breaks down each of the 3 BPS items, what the scores actually look like at the bedside, why the BPS only makes sense alongside the RASS, and what a defensible BPS chart entry includes.
Why This Matters
Regulatory bodies: Society of Critical Care Medicine (SCCM) - 2018 PADIS Clinical Practice Guidelines, American Association of Critical-Care Nurses (AACN), The Joint Commission - Pain Assessment and Management Standards, CMS Hospital Conditions of Participation - Pain Management
- Assessing pain in critically ill sedated patients by using a behavioral pain scale — Payen JF, Bru O, Bosson JL, et al. Crit Care Med. 2001;29(12):2258-2263 (2001)
- Clinical Practice Guidelines for the Prevention and Management of Pain, Agitation/Sedation, Delirium, Immobility, and Sleep Disruption in Adult Patients in the ICU (PADIS) — Devlin JW, Skrobik Y, Gelinas C, et al. Society of Critical Care Medicine. Crit Care Med. 2018;46(9):e825-e873 (2018)
- Behavioral Pain Scale (BPS) for Pain Assessment in Intubated Patients — MDCalc (2024)
- R3 Report Issue 11: Pain Assessment and Management Standards for Hospitals — The Joint Commission (2017)
What the BPS is and when to use it
The 3 BPS items
What each item scores at the bedside, with the specific behaviors that distinguish 1, 2, 3, and 4.
Item 1 - Facial expression (1 to 4)
Item 2 - Upper limb movements (1 to 4)
Item 3 - Compliance with mechanical ventilation (1 to 4)
Charting the total and the items
How nurses document a BPS score in the ICU
The score is the easy part. Documenting it in a way that drives titration and reassessment is the part that matters.
BPS vs CPOT vs FLACC vs PAINAD and the 0 to 10 numeric scale
Picking the right tool for your patient is more important than picking one you already know.
Self-report (0 to 10 numeric or pointing to a card) first
BPS for intubated, sedated adult ICU patients
CPOT for non-intubated critically ill adult ICU patients
FLACC for pediatric and cognitively impaired patients
PAINAD for non-verbal patients with advanced dementia
BPS in NurseChartingPro
Common Mistakes
Charting BPS without the current RASS
A BPS score in isolation does not tell the next nurse whether the patient is comfortable or whether the score reflects sedation depth. RASS context is what makes the BPS interpretable. A low BPS at RASS -4 is not the same clinical picture as a low BPS at RASS 0, and the chart should reflect the difference.
Scoring upper-limb movement on a paralyzed patient
Upper-limb movement is meaningless under continuous paralysis. Recording 1 on the upper-limb item misrepresents the assessment and can hide undertreated pain. Document that BPS is not applicable, and use physiologic surrogates and BIS while the patient is paralyzed.
Treating a BPS of 6 or 7 as "fine" because the patient is sedated
A BPS of 6 or higher is the published threshold for unacceptable pain in the original Payen scoring framework. Continuing the same regimen because the patient is "sedated" misses the point: the patient is sedated AND in pain, and the right move is analgesia first, not more sedation. SCCM 2018 PADIS specifically calls out the analgesia-first approach.
Skipping reassessment after the IV opioid bolus
IV opioid reassessment is a clinical and a legal requirement. A bolus given without a documented reassessment score is an incomplete pain management record and a common ICU survey finding. The reassessment also tells the provider whether the bolus was effective and whether the continuous infusion should be re-titrated.
Mixing BPS with the 0 to 10 numeric scale in the same entry
BPS and the 0 to 10 numeric scale are different instruments with different validation populations and different score ranges (BPS is 3 to 12, not 0 to 10). Writing "7/10 (BPS)" conflates them and makes chart audit and trend tracking harder. The total is on a 3 to 12 range, but the scale is BPS, not numeric.
Using BPS on a non-intubated patient who can self-report
Using BPS on a patient who can self-report is the same error as using FLACC on a cooperative 10 year old: it produces a documented score that does not reflect the actual patient experience, and it undercuts the validity of the assessment. Self-report is the gold standard whenever it is available.
Case Example
Scenario
You are the day shift surgical ICU nurse. Mr. Alvarez came up from the OR overnight after an open AAA repair and is intubated on volume-control ventilation. He is on propofol 30 mcg/kg/min and fentanyl 50 mcg/h continuous infusion. The night nurse charted a BPS of 5 at 0400 with a RASS of -2. At 0800, you are starting your assessment when respiratory comes in to suction the endotracheal tube. During suctioning you watch his face, his arms, and the ventilator together for 1 full minute.
Chart Entry
Pain assessment 0800:

BPS total: 9
- Facial expression: 4 - sustained grimace, brow locked, eyelids tightly closed
- Upper limb movements: 3 - both arms drawn up at the elbows with finger flexion during suctioning
- Compliance with mechanical ventilation: 2 - coughing during suctioning, returns to synchrony between passes

Clinical context: RASS 0 during suctioning, RASS -1 at rest. Currently on propofol 30 mcg/kg/min, fentanyl 50 mcg/h. Day 1 post-AAA repair with midline laparotomy incision.

Intervention: fentanyl 50 mcg IV bolus delivered at 0802; suctioning paused after 2 passes; bedside coached on pre-suction bolus timing for next pass.

Reassessment at 0830: BPS 4 (Face 2 - mild brow lowering at rest, Upper limbs 1 - arms relaxed, Vent compliance 1 - tolerating ventilation). RASS -2. Continuous fentanyl rate increased from 50 to 75 mcg/h per ICU pain protocol; will reassess at 0900 and PRN with stimulation.
Key points from above chart entry
- Item breakdown documented:
- All 3 item scores are listed individually so the next nurse sees the pain presents as a facial-and-upper-limb pattern, not as ventilator dyssynchrony alone.
- RASS paired with every BPS:
- The BPS is interpretable only against the current RASS. A 9 at RASS 0 is severe pain; a 9 would mean something different at RASS -4. The chart entry pairs them at every measurement.
- Bolus + reassessment within 30 minutes:
- Fentanyl bolus at 0802, reassess at 0830 - within the standard 30-minute post-IV-opioid window. The reassessment score is the documentation that closes the loop.
- Continuous rate adjusted, not just the bolus:
- A high BPS during a stimulus suggests the baseline analgesia is not adequate. The continuous fentanyl rate was increased per protocol, and the reason is in the chart so the provider can verify the change on rounds.
- No self-report attempted because the patient is intubated and sedated:
- The chart does not show a self-report attempt because the patient is on propofol and intubated. The trigger for using BPS is recorded in context.
Pro Tips
- Always pair BPS with the current RASS: A BPS without a RASS is a number with no scale. Document both at every assessment. A high BPS in a deeply sedated patient is more concerning than a high BPS at RASS 0 because the patient is showing pain through the sedation. A low BPS in an over-sedated patient may be hiding pain that the patient cannot express.
- Score during a stimulus, not just at rest: Pain in a sedated patient often shows up only during a stimulus: suctioning, repositioning, dressing change, line insertion. If you score BPS only at rest, you may miss the procedural pain that drives the analgesic regimen. Score during the stimulus and document the trigger ("BPS 9 during ETT suctioning"), then again at rest after the intervention.
- Watch the ventilator waveforms, not just the alarms: Ventilator-compliance scoring is more accurate when you watch the waveforms during one full breath cycle than when you glance at the alarm history. Dyssynchrony does not always trigger an audible alarm, especially in newer vents that auto-adjust trigger sensitivity. Asking the RT to look at the screen with you for 30 seconds is faster than chasing alarms.
- Document BPS as not applicable on paralyzed patients: On a continuous paralytic, the upper-limb item is uninformative and the vent-compliance item is partially confounded by the paralytic itself. Document "BPS not applicable, patient on continuous neuromuscular blockade" and use physiologic surrogates plus BIS or processed EEG. Resume BPS scoring when the paralytic is held for the daily neuro check.
- Pair every IV opioid BPS with a reassessment within 30 minutes: The reassessment score is what closes the clinical and legal loop. Document the intervention time, the reassessment time, and the new BPS plus RASS. An IV opioid given without a documented reassessment score is a survey finding waiting to happen, and in the ICU it is also an analgesic-titration moment that can prevent the next stimulus from spiking the score again.
Step by Step
- Confirm BPS is the right tool for this patient: If the patient can mouth a number, point to a card, or blink reliably to a yes-or-no scale, use a self-report tool instead. If the patient is intubated and sedated, BPS is appropriate. If extubated and nonverbal, use BPS-NI. If on continuous paralysis, document BPS not applicable.
- Note the current RASS first: Document the Richmond Agitation-Sedation Scale (RASS) score at the time of the BPS assessment. The two scores are read together; the BPS is not interpretable without the sedation context.
- Observe the patient for one full breath cycle, ideally during a stimulus: Watch the face, the upper limbs, and the ventilator waveforms together. Pain in a sedated patient often shows up only during a stimulus (suctioning, turning, dressing change), so include the trigger in the chart.
- Score each of the 3 items 1 to 4: Facial expression, upper limb movements, and compliance with mechanical ventilation each get a 1, 2, 3, or 4 based on the published rubric. For BPS-NI (the non-intubated version), replace the ventilator item with vocalization.
- Sum the items for a total of 3 to 12: Total 3 = no pain. 4 to 5 = mild pain. 6 to 8 = unacceptable pain warranting analgesic adjustment. 9 to 12 = severe pain warranting escalation.
- Intervene and reassess: For scores 6 and above, apply a pain intervention per your facility's intensive care unit (ICU) pain protocol, such as an as-needed (PRN) intravenous (IV) opioid, a continuous-infusion rate adjustment, a nonpharmacologic measure, or provider notification. Reassess the BPS within the window appropriate to the intervention (15 to 30 minutes for IV opioid bolus) and document the new score plus the current Richmond Agitation-Sedation Scale (RASS) score.
Frequently Asked Questions
- What does a BPS score of 6 mean?
- A BPS of 6 is the published threshold for unacceptable pain in the original Payen 2001 scoring framework. It should prompt a review of the analgesic regimen, an intervention if clinically appropriate, and a reassessment within the intravenous (IV) opioid window (15 to 30 minutes after a bolus). A 6 is not a "wait and see" score; it is a score that should drive a decision.
- Is BPS only for intubated patients?
- BPS as published is only for intubated, sedated adult intensive care unit (ICU) patients. BPS-NI (non-intubated) is the parallel scale for non-intubated patients who still cannot self-report; it substitutes vocalization for the ventilator-compliance item and preserves the same 3 to 12 range and the same unacceptable-pain threshold of 6. Use BPS for intubated patients and BPS-NI for non-intubated nonverbal adults. For pediatric patients, use FLACC (Face, Legs, Activity, Cry, Consolability). For non-verbal advanced-dementia patients outside the ICU, use PAINAD (Pain Assessment in Advanced Dementia).
- How is BPS different from the numeric 0 to 10 pain scale?
- BPS differs from the numeric 0 to 10 pain scale because the numeric scale is a self-report tool, where the patient states their pain intensity, and BPS is an observational tool, where the nurse rates 3 behavioral items the patient displays. The score ranges are also different (BPS is 3 to 12, not 0 to 10), so the numeric values are not interchangeable. Self-report is preferred when the patient can mouth a number, point to a card, or blink reliably; BPS is a fallback for patients who cannot self-report. Do not use both tools on the same patient at the same time or mix their scores in a single chart entry.
- Why do I need to chart RASS with every BPS?
- Chart the Richmond Agitation-Sedation Scale (RASS) with every BPS because the BPS items depend on the patient being able to grimace, move the arms, and react to the ventilator, and a deeply sedated patient may not show those behaviors even when they are in pain. A BPS of 3 at RASS -4 is not the same clinical picture as a BPS of 3 at RASS 0. The 2018 Society of Critical Care Medicine (SCCM) pain, agitation/sedation, delirium, immobility, and sleep disruption (PADIS) guidelines and most intensive care unit (ICU) pain protocols expect both numbers paired in the chart so the next nurse and the provider can interpret the pain finding against the sedation depth.
- How often should I reassess with BPS after an IV opioid?
- After an intravenous (IV) opioid bolus (fentanyl, morphine, hydromorphone), reassess the BPS within 15 to 30 minutes. Reassessment timing follows the medication and your facility policy, not the BPS tool itself. After a continuous-infusion rate change, reassess within 30 to 60 minutes once the new rate has reached steady state. Document the reassessment BPS with the time and the current Richmond Agitation-Sedation Scale (RASS) score; an intervention without a reassessment score is an incomplete intensive care unit (ICU) pain record.
- Can BPS be used on a patient with continuous neuromuscular blockade?
- No, BPS cannot be validly scored on a patient with continuous neuromuscular blockade. The upper-limb-movement item is uninformative under continuous paralysis, and the ventilator-compliance item is partially confounded by the paralytic. Document "BPS not applicable, patient on continuous neuromuscular blockade" and use physiologic surrogates (heart rate, blood pressure trends, lacrimation) plus a processed electroencephalogram (EEG) sedation monitor, such as the bispectral index (BIS) or SedLine, per facility policy. Resume BPS scoring when the paralytic is held for the daily neuro check or stopped.
Get the free Nursing Charting Cheat Sheet
- All 16 charting categories, clinical and psych, with what to write for each
- Morse, Braden, Glasgow Coma Scale and SBAR at a glance
- The charting mistakes that cost nurses their licenses
Chart faster with Nurse Charting Pro
Tap through your assessments during the shift and get a draft of your note to review at clock-out. Your notes are cleared from your phone at the end of your shift.
Related Guides
- Clinical nursing chartingThe 8 clinical charting categories, including where pain scores fit in the shift.
- CPOT pain scale documentationThe parallel adult ICU behavioral pain tool. CPOT scores 4 items on a 0 to 8 range and is the alternative to BPS in many adult ICUs. Use CPOT or BPS, not both.
- PAINAD pain scale for advanced dementiaThe behavioral pain tool for non-verbal advanced-dementia patients in med-surg, long-term care, and memory care. Different population, different range (0 to 10), same documentation rhythm.
- FLACC pain scale for pediatric and cognitively impaired patientsThe behavioral pain tool for children ages 2 months to 7 years and for cognitively impaired patients outside the adult ICU. Different population, different range (0 to 10), same documentation rhythm.
- Richmond Agitation-Sedation Scale documentationBPS is interpretable only against the current RASS. The RASS guide covers the sedation-depth side of the pain-and-sedation pairing every adult ICU charts together.
- Skin and Wound charting (pain block)BPS is selectable in the pain block of the Skin and Wound assessment in NurseChartingPro; see the full pain-documentation walkthrough for the structured-field flow.