By Miranda Niemas, Nursing Student (BSN candidate)
This guide is currently pending review by a licensed registered nurse.
Last updated: October 13, 2026
How to Score and Document a RASS Assessment (Nursing Guide)
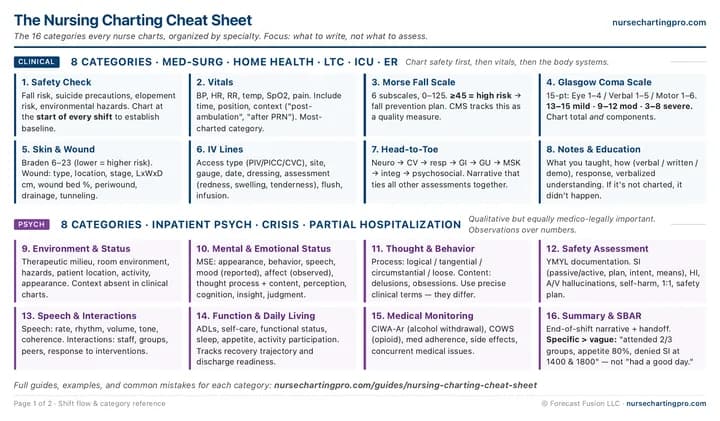
Get the free Nursing Charting Cheat Sheet
- All 16 charting categories, clinical and psych, with what to write for each
- Morse, Braden, Glasgow Coma Scale and SBAR at a glance
- The charting mistakes that cost nurses their licenses
Your post-op patient is on a propofol drip with a target RASS of -2 to 0. The night nurse charted RASS -3 at 0400, and the intensivist on rounds wants to know whether the gtt should come down before extubation. I sat through this exact scenario in my critical-care rotation last semester. The framework that finally made it click is the three-step assessment, observe then voice then physical, scored top down from +4 to -5.
Why This Matters
Regulatory bodies: Society of Critical Care Medicine (SCCM) - PADIS Guidelines, American Association of Critical-Care Nurses (AACN), The Joint Commission - Sedation and Anesthesia Care Standards, Vanderbilt ICU Delirium and Cognitive Impairment Study Group
- The Richmond Agitation-Sedation Scale: validity and reliability in adult intensive care unit patients — Sessler CN, Gosnell MS, Grap MJ, et al. Am J Respir Crit Care Med. 2002;166(10):1338-1344 (2002)
- Monitoring sedation status over time in ICU patients: reliability and validity of the Richmond Agitation-Sedation Scale (RASS) — Ely EW, Truman B, Shintani A, et al. JAMA. 2003;289(22):2983-2991 (2003)
- Clinical Practice Guidelines for the Prevention and Management of Pain, Agitation/Sedation, Delirium, Immobility, and Sleep Disruption in Adult Patients in the ICU (PADIS) — Devlin JW, Skrobik Y, Gelinas C, et al. Crit Care Med. 2018;46(9):e825-e873 (2018)
- Monitoring Delirium in the ICU - RASS and CAM-ICU implementation guidance — Vanderbilt ICU Delirium and Cognitive Impairment Study Group (CIBS Center) (2024)
What the Richmond Agitation-Sedation Scale Measures
The 10 Levels of RASS, Scored Top Down
Read the scale from +4 down to -5. The first descriptor that matches the patient indicates the score.
+4 Combative
+3 Very Agitated
+2 Agitated
+1 Restless
0 Alert and Calm
-1 Drowsy
-2 Light Sedation
-3 Moderate Sedation
-4 Deep Sedation
-5 Unarousable
The Three-Step Assessment Procedure
How Nurses Document a RASS Score
RASS, Target Sedation Bands, and the Sedation Interruption Decision
Sedation Documentation in NurseChartingPro
Common Mistakes
Charting Only the Number Without the Stimulus
RASS without the stimulus provides only part of the score. The next nurse cannot determine whether the patient was unresponsive to physical stimulation or simply not yet escalated past voice. Document the highest stimulus used.
Confusing -2 (Light Sedation) With -3 (Moderate Sedation)
The clinical distinction between -2 and -3 hinges on eye contact, not just duration. Brief eye contact lasting under 10 seconds indicates -2; movement or eye opening to voice without eye contact indicates -3. Scoring as "drowsy" without specifying eye contact leads to scoring errors.
Skipping Observation and Going Straight to Voice
Scores +4 through 0 should be assigned by observation alone. Adding a voice or physical stimulus the patient did not need overestimates arousal and undertreats agitation.
Charting RASS Without the Target Band
RASS -1 may indicate light sedation, target sedation, or deep sedation based on the team's sedation goal for the patient. Without the target band in your chart entry, the next reader cannot determine whether your action or inaction was appropriate.
Performing CAM-ICU on a Patient at RASS -4 or -5
CAM-ICU requires patient participation in attention testing, meaning RASS -3 or above. Documenting a CAM-ICU negative for a deeply sedated patient yields a meaningless result and undermines the chart. Follow the protocol: assess RASS first, then perform CAM-ICU only if the patient is arousable enough for testing.
Case Example
Scenario
As the day shift ICU nurse, you are caring for Mr. Hayes, who was admitted overnight after an open AAA repair. He is intubated on assist control with a propofol gtt at 30 mcg/kg/min and a fentanyl PCA. The night shift's last RASS at 0500 was -3. The intensivist plans to extubate this morning and asks you to titrate to a SAT goal of RASS -1 to 0 by 0900 rounds.
Chart Entry
0800 Sedation Assessment:

RASS -3 to voice. Eyes opened briefly without sustained eye contact, no movement.
Stimulus: stated "Mr. Hayes, open your eyes and look at me" twice.
Target band: -1 to 0 (SAT goal per intensivist for planned extubation).
Action: propofol gtt decreased from 30 to 20 mcg/kg/min per protocol. Fentanyl PCA continued unchanged.
Reassess RASS in 30 minutes.

0830 Sedation Reassessment:

RASS -2 to voice. Brief eye contact for approximately 4 seconds, no sustained tracking.
Stimulus: voice only.
Target band: -1 to 0.
Action: propofol gtt decreased to 10 mcg/kg/min.
Reassess RASS in 30 minutes.

0900 Sedation Reassessment:

RASS -1 to voice. Sustained eye contact for 15 seconds, follows the command "squeeze my hand" bilaterally, no agitation, no aggressive movement.
Stimulus: voice only.
Target band: -1 to 0 (within target).
CAM-ICU: negative (RASS now within validity range).
Action: propofol gtt held per SAT protocol. Intensivist notified at 0902 for SBT and extubation assessment. Patient comfortable, vent triggering well, no signs of pain on CPOT.
Key points from above chart entry
- Stimulus documented at every score:
- Each entry names the stimulus used (voice, with the exact phrase) so the next reader can reproduce the assessment.
- Target band on every entry:
- The SAT goal of -1 to 0 appears in every reassessment, showing the team is titrating toward a defined endpoint.
- Reassessment timing tied to titration:
- Each titration is followed by a 30-minute RASS reassessment, demonstrating the expected score-titrate-reassess loop in ICU sedation.
- CAM-ICU sequenced after RASS:
- CAM-ICU is documented only after RASS reaches -1, which is within the validity range. A negative CAM-ICU at RASS -3 would have been uninterpretable.
- SAT outcome documented:
- The 0900 entry shows the SAT goal was reached, the gtt was held, and the team was notified, closing the SAT documentation loop.
Pro Tips
- Always Score Top Down, Not Bottom Up: Read the RASS from +4 down to -5 and assign the first descriptor that matches the patient. Scoring bottom-up, such as asking "Is this -2 or -3?", increases the risk of misclassification because it skips the agitation tier entirely.
- The 10-Second Eye Contact Rule Is Real, Count It: The clinical distinction between RASS -1 and -2 hinges on whether eye contact lasts 10 seconds or longer. Count silently in your head; don't estimate visually. The titration decision related to RASS -1 versus -2 varies across most ICU sedation protocols, and the eye contact rule serves as the deciding factor.
- Document the Target Band on Every RASS Entry: A bare RASS score fails to inform the next reader whether your action was correct. Always pair each RASS with the target band the team set. This simple addition transforms the chart entry from a snapshot into an action-oriented note that can withstand a chart audit.
- Reassess Within 30 Minutes of Every Continuous Sedative Titration: RASS is not a once-a-shift assessment when a continuous sedative is running. Every titration generates a new reassessment within 15 to 30 minutes, documented with the new score. This was the habit my critical-care clinical instructor drilled into us, and the chart pattern is what proves the titration was effective.
- Pair RASS With CAM-ICU Only When RASS Is -3 or Higher: CAM-ICU requires patient participation in attention testing. A patient with a RASS of -4 or -5 cannot participate, making a CAM-ICU negative result on a deeply sedated patient meaningless and careless. Start with RASS; use CAM-ICU only if the patient is arousable enough for testing.
Step by Step
- Observe the patient first: Observe the patient at the bedside without speaking or touching. You can determine your score (+4 through 0) based on their behavior: overtly combative, very agitated, agitated, restless, or alert and calm.
- Escalate to voice if no observable score: When the patient appears asleep or unresponsive, state their name and ask them to open their eyes and look at you. The eye contact response gives the score: sustained eye contact for 10 seconds or longer is -1, brief eye contact under 10 seconds is -2, and movement or eye opening without eye contact is -3.
- Escalate to physical stimulation if no response to voice: If the patient does not respond to voice, apply a physical stimulus like a shoulder shake or trapezius squeeze. Movement or eye opening in response to physical stimulation scores -4, while no response scores -5. Document the specific stimulus used.
- Document the score with stimulus and target band: Chart the time, score, stimulus that produced it, team's target sedation band, and action taken (titration up, down, or no change).
- Reassess after every titration: After any continuous sedative titration, reassess the RASS within 15 to 30 minutes. Document the new score. This process closes the score-titrate-reassess loop and shows that the intervention achieved its intended effect.
Frequently Asked Questions
- What does RASS stand for?
- RASS stands for Richmond Agitation-Sedation Scale. This 10-point bedside scale assesses sedation and agitation. Sessler and colleagues developed it at Virginia Commonwealth University in 2002, validating it for inter-rater reliability in adult intensive care unit (ICU) patients across medical and surgical ICUs.
- What is the RASS scoring range?
- RASS scores range from -5 (unarousable, no response to voice or physical stimulation) to +4 (combative, immediate danger to staff), with 0 representing alert and calm. The negative scores measure depth of sedation; the positive scores measure severity of agitation.
- What is the difference between RASS -2 and RASS -3?
- The distinction between -2 (light sedation) and -3 (moderate sedation) lies in eye contact. A score of -2 applies when the patient briefly opens their eyes and makes eye contact in response to voice for less than 10 seconds. In contrast, a score of -3 occurs if the patient opens their eyes or moves in response to voice but does not establish eye contact. Eye contact, not its duration, is the deciding factor; the 10-second rule separates -1 from -2.
- Should RASS be done before or after CAM-ICU?
- Always perform RASS before CAM-ICU. The Confusion Assessment Method for the Intensive Care Unit (CAM-ICU) is valid only if the patient is arousable (RASS -3 or higher). Patients at RASS -4 or -5 cannot complete CAM-ICU. A negative CAM-ICU documented on a deeply sedated patient cannot be interpreted and is flagged in chart audits.
- Is RASS validated for procedural sedation or pediatric patients?
- No, RASS was developed and validated specifically for adult intensive care unit (ICU) patients. For procedural sedation, use the Modified Observer's Assessment of Alertness/Sedation (MOAA/S). In pediatric ICU patients, use the State Behavioral Scale (SBS) or the Comfort-B scale. Using RASS outside its validated population may produce scores that appear clean but do not accurately reflect the patient's condition.
Get the free Nursing Charting Cheat Sheet
- All 16 charting categories, clinical and psych, with what to write for each
- Morse, Braden, Glasgow Coma Scale and SBAR at a glance
- The charting mistakes that cost nurses their licenses
Chart faster with Nurse Charting Pro
Tap through your assessments during the shift and get a draft of your note to review at clock-out. Your notes are cleared from your phone at the end of your shift.
Related Guides
- CIWA-Ar withdrawal documentationThe closest sibling guide for alcohol withdrawal. Withdrawal scoring follows a score-intervene-reassess loop currently used in NCP. RASS shares this documentation rhythm.
- COWS withdrawal documentationThe opioid counterpart. Same score-intervene-reassess loop and the same trigger-and-response discipline as RASS.
- how to score and document Glasgow Coma ScaleThe other major bedside neuro-status scale. GCS measures consciousness; RASS measures sedation depth and agitation. Both share the trapezius-squeeze stimulus and the trend-over-time documentation pattern.
- FLACC pain scale documentationPain assessment in nonverbal or sedated patients. Many ICUs pair CPOT (the adult ICU equivalent of FLACC) with RASS to capture pain and sedation together at every assessment.
- the SBAR handoff frameworkRASS, the target sedation band, and the most recent titration should appear in the Background and Assessment of any ICU SBAR.
- clinical nursing charting overviewRASS plays a crucial role in the broader clinical documentation framework. The hub page connects to every clinical category guide.