By Amy Niemas, RN-BC, BSN, MSW, Clinical Content Director · Psychiatric Registered Nurse
Last updated: October 13, 2026
How to Chart Patient Restraints and the Post-Restraint Evaluation
The federal requirements described here come from 42 CFR 482.13, which applies to hospitals, so if you work in long-term care or home health your setting is governed by different regulations and your facility policy is the standard to follow.
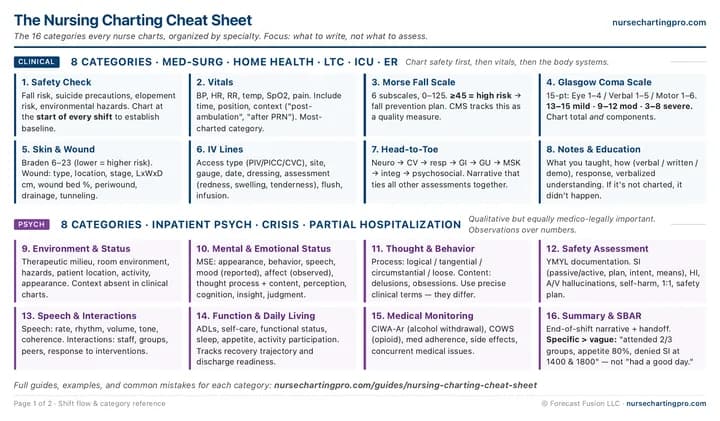
Get the free Nursing Charting Cheat Sheet
- All 16 charting categories, clinical and psych, with what to write for each
- Morse, Braden, Glasgow Coma Scale and SBAR at a glance
- The charting mistakes that cost nurses their licenses
Why This Matters
Regulatory bodies: CMS Conditions of Participation, Joint Commission Hospital Standards, State Boards of Nursing
- 42 CFR 482.13, Condition of Participation: Patient's Rights — Cornell Law School, Legal Information Institute
- Understanding the new standards for patient restraint and seclusion — American Nurse Journal
- Assessing and documenting patient restraint incidents (Woodard J.) — American Nurse Journal (2015)
- State Operations Manual, Appendix A: hospital interpretive guidelines for 42 CFR 482.13 — Centers for Medicare & Medicaid Services (CMS)
- Nurse case study: alleged failure to properly assess and monitor the impaired, restrained patient — Nurses Service Organization (NSO)
Categories and Types of Restraints
The Restraint Order: Time Limits, Renewals, and the Absence of PRN Restraint
The 1-Hour Face-to-Face Evaluation
What to Chart at Initiation of Restraints
The Monitoring Flowsheet: What to Include in Every Entry
Discontinuation and Post-Restraint Evaluation
Common Mistakes
Charting Only the Restraint
The weak version does not explain the reason for the restraint, leaving reviewers unable to determine what happened, or whether the restraint was justified. Documenting the behavior, the alternatives attempted, and the provider order for the restraint are all essential elements.
PRN Restraint Orders
Federal regulation prohibits standing orders or PRN orders for restraints. Each episode requires a current, time-limited order, and behavioral orders expire based on the 4/2/1-hour age tiers (4 hours for adults, 2 hours for adolescents, and 1 hour for children). If you see a PRN restraint order, clarify it with the provider.
Leaving Gaps in the Monitoring Flowsheet Without Explanation
A blank interval suggests monitoring never occurred, and no reviewer will assume otherwise. If a check was missed or charted late, document the time and reason. In psychiatric settings, also document that the patient remained under continuous observation with a 1:1 sitter or safety assistant. This shows that the patient was never left unattended, even if a documentation entry was missed.
Skipping the Consult Note After an RN Face-to-Face
When a trained RN performs the 1-hour face-to-face for violent/behavioral restraint, regulations require that the attending physician or another licensed practitioner is contacted as soon as possible afterwards. An evaluation note without the consult note creates a documentation gap, even if the evaluation itself was timely.
Ending the Chart at the Last Monitoring Check
Discontinuation is a required part of the episode record: document the release time, condition (mental and physical) at release, injury check, and the debrief. A restraint record that simply stops leaves the reviewer guessing when and how the episode ended. The debrief is the element that is most often omitted from charts, even though most facilities require it.
Case Example
Scenario
Marcus is a fictional 32-year-old male admitted to the inpatient psychiatric unit for acute psychosis. At 1410, he begins pacing and yelling, throws items in his room, slams his door, and overturns a bedside table. Verbal de-escalation is attempted but unsuccessful, and he refuses an offered PRN medication. He then hits a CNA with a closed fist. Staff apply bilateral four-point restraints at 1415 while the nurse obtains an order for the restraints. He calms over the next hour, and restraints are discontinued at 1545.
Chart Entry
1410: Patient pacing and yelling after phone call. Throwing items around room, slamming door, and overturning bedside table. Also cursing at staff. Verbal de-escalation and redirection attempted multiple times by this RN, charge RN, and floor staff, but patient not responsive to this. Also offered PO lorazepam per existing order, patient refused. Behavior continued to escalate. Postured at staff and hit CNA in the face with a closed fist.
1415: Patient escorted to bed by staff, bilateral four-point restraints applied for violent behavior endangering staff. 1:1 safety assistant initiated.
1422: Provider notified, verbal order received for restraints. Will monitor according to facility guidelines.
1500: 1-hour face-to-face evaluation completed by this RN. Patient oriented x4, somewhat less agitated, but still pulling on restraints and cursing at staff. Denies pain, skin intact, circulation intact. Continued restraint warranted due to intermittent pulling and threats toward staff. Provider consulted by phone at 1510, agrees with plan. Patient remains with 1:1 sitter/safety assistant.
1545: Restraints discontinued. Patient has had 30 minutes of calm, cooperative behavior and is contracting for safety. Serial release of restraints performed. Patient maintained appropriate behavior throughout. Skin intact at restraint sites, circulation and sensation intact, full ROM, no injuries observed. Debrief completed with patient: identifies phone calls as a trigger, agrees to request staff support earlier and take PRN medication should he become upset again. Care plan updated, provider and oncoming nursing staff notified.
Key points from above chart entry
- Behavior in observable terms:
- The 1410 entry records what Marcus did (threw, slammed, overturned, cursed), not a label like "aggressive." The observable behavior is what justifies a behavioral restraint and everything that follows.
- Alternatives before restraint:
- De-escalation attempts and the refused PRN medication are charted with outcomes. "Less restrictive interventions attempted" is a required element, and this is where it is documented in the chart.
- Honest order timing:
- Restraints at 1415, verbal order at 1422. Emergency application of restraints before the order is received is expected; the chart shows the real sequence.
- Face-to-face plus consult:
- The 1500 entry documents both the RN-performed 1-hour evaluation and the 1510 provider consult. The consult note is the half that is often left out in charting.
- Discontinuation and debrief:
- The 1545 entry closes the episode: release rationale, condition (mental and physical) and injury check, the debrief with what the patient identified, and the care plan updated. This is the post-restraint evaluation in practice.
Pro Tips
- The order will almost always come after the restraint, and your charting should say so: In a true emergency, restrain first and then obtain the order as soon as possible. This sequence is expected and compliant. A chart that falsely suggests the order came first lacks defensibility and credibility. Document the actual times. The honest sequence protects you; the altered one risks scrutiny during review.
- Document the missed check and its reason: When a monitoring check is missed, document the omission, including when it occurred and the reason. Missed checks can occur, but not documenting it and the reason why it was missed can trigger a much more serious investigation.
- Know which clock is federal and which is your facility's: The 4/2/1-hour order tiers (adult/adolescent/child), the 24-hour see-and-reassess by a provider, and the 1-hour face-to-face are federal requirements. In contrast, the every-15-minute flowsheet interval follows your facility's policy, which is based on a federal rule that allows hospitals to set their own frequency. Review your facility's restraint policy during orientation and make sure that you can locate it when needed; it is the standard against which your chart is audited, and reading it once beats any amount of guessing. Also remember the differences in psychiatric/violent restraints versus non-violent/med-surg restraints.
- Treat the debrief as an essential part of the process, not just as more paperwork: Nurses often skip the debrief entry, yet it serves as one of the only opportunities to prevent future incidents. Document what the patient identifies as triggers for escalation and note strategies that could help earlier. Include this information in the care plan and communicate it during report. A restraint episode that does not lead to changes in the plan is likely to repeat.
Step by Step
- Classify the restraint: Document the type of restraint used (physical/mechanical, manual, chemical, or environmental/seclusion) and classify the episode as either violent/psychiatric (behavioral) or non-violent (med-surg) restraint according to the patient's behavior. This classification determines the order time limits, the face-to-face requirement, and the monitoring guidelines. Follow your facility's procedures for category names.
- Chart the behavior and the alternatives at initiation: Chart the specific observable behavior that necessitated the restraint and note every less-restrictive intervention attempted first, along with the patient's response to each.
- Secure and document the time-limited order: Obtain this order as soon as possible after emergency application if needed, and document the exact times for both the application and the order. Behavioral orders expire at 4 hours for adults, 2 hours for adolescents, and 1 hour for children. No restraint order is ever as needed (PRN) or standing.
- Complete and document the 1-hour face-to-face (behavioral only): A qualified evaluator, meaning a physician, other licensed practitioner, or trained registered nurse as your facility defines it, must see the patient face-to-face within 1 hour of initiation and document the evaluation. If a registered nurse performs the evaluation, the nurse consults the provider as soon as possible and charts that consult.
- Chart monitoring at your facility's interval: Document every flowsheet element at each interval: behavior, mental status, restraint placement, circulation and sensation, range of motion, vital signs, skin, and food/fluid/toileting offered. In psychiatric settings, also document that the patient remained under continuous observation with a 1:1 sitter or safety assistant. If you miss or are late for a check, note it honestly, including the time and reason.
- Document discontinuation of restraints and the debrief: Document the release time, the behavior justifying release, the patient's condition and injury check, and the post-restraint debrief with the patient, and carry the triggers and preferences into the care plan and the handoff.
Frequently Asked Questions
- Does every restraint need a 1-hour face-to-face evaluation?
- No, not every restraint needs a 1-hour face-to-face evaluation; it applies only to restraint or seclusion used for violent/psychiatric (behavioral) reasons. Non-violent med-surg restraints, like soft wrist restraints or mittens on a confused patient pulling at lines, do not trigger this requirement under the federal hospital rule (42 CFR 482.13). Your facility's policy sets the assessment schedule for non-violent restraint.
- Can a registered nurse perform the 1-hour face-to-face?
- Yes, a registered nurse trained under the hospital's program may perform the 1-hour face-to-face for violent/psychiatric restraint. The nurse must then consult the provider responsible for the patient's care (the physician or other licensed practitioner) as soon as possible afterward, and the consult must be documented. Follow your facility's guidelines for who qualifies to do the 1-hour evaluation.
- How often do I need to chart on a restrained patient?
- Chart on a restrained patient at the interval your facility's policy sets; federal regulation requires monitoring "at an interval determined by hospital policy." The common convention is an entry every 15 minutes for violent/psychiatric restraint and every 2 hours for non-violent/med-surg restraint, but your facility's policy sets the interval your chart is audited against, so read it rather than assuming. In psychiatric settings, the 1:1 sitter or safety assistant stays with the patient continuously even though the chart entry may only be made every 15 minutes.
- Do restraint orders expire?
- Yes, restraint orders expire. Violent/psychiatric restraint orders expire at 4 hours for adults 18 and older, 2 hours for ages 9 to 17, and 1 hour for children under 9, renewable up to 24 hours. After 24 hours, a physician or other licensed practitioner must personally see and assess the patient before a new order can be placed. Restraint orders can never be as needed (PRN) or standing. Non-violent restraint order renewal follows hospital policy. An unexpired order does not replace ongoing reassessment, which continues for as long as the restraint is in place.
- What do I chart when restraints come off?
- Chart the time of release, the behavior justifying the release, and the patient's behavior and condition, including a skin and circulation check of the restrained extremities. Document any injuries found and vital signs per policy. Include the post-restraint debrief: what happened, what the patient identifies as triggers, what coping skills the patient can use in the future, and what will go into the care plan to prevent or limit repeat occurrences.
Get the free Nursing Charting Cheat Sheet
- All 16 charting categories, clinical and psych, with what to write for each
- Morse, Braden, Glasgow Coma Scale and SBAR at a glance
- The charting mistakes that cost nurses their licenses
Chart faster with Nurse Charting Pro
Tap through your assessments during the shift and get a draft of your note to review at clock-out. Your notes are cleared from your phone at the end of your shift.
Related Guides
- Clinical nursing chartingThe 8 clinical charting categories, for non-violent (medical) restraint settings.
- Psychiatric nursing chartingThe 8 psych charting categories, for violent or self-destructive behavior restraint and seclusion.
- Safety assessment documentation (SI, HI, and 1:1 observation)The documentation that runs alongside a behavioral restraint episode: suicidal and homicidal ideation screening, observation levels, and safety monitoring.
- Safety check charting for clinical unitsRoutine safety and rounding documentation; the everyday counterpart to the restraint monitoring flowsheet.
- Charting mistakes that can cost your nursing licenseThe license-anxiety companion piece: which documentation errors carry real consequences and which fears are exaggerated.
- The SBAR handoff frameworkHand off a patient restraint episode by explaining it to the next shift before they review the chart.
- The complete nursing charting cheat sheetThe scannable documentation reference across every charting category.